


Yes, ovulation tests can be useful with endometriosis, but a positive result is a timing clue, not a complete fertility check. An ovulation predictor kit (OPK) detects a rise in luteinising hormone (LH) in urine. It cannot prove that an egg was released or show whether endometriosis is affecting other steps needed for pregnancy.
That distinction matters whether you are seeing a clear positive, a faint line every day or no surge at all. The next step is to decide whether testing suits your treatment, whether the result was valid and whether you need help with timing or a broader assessment.
Quick answers about ovulation tests and endometriosis
Do ovulation tests work with endometriosis?
They can help with timing in a natural cycle by detecting a rise in urinary luteinising hormone, or LH. Endometriosis does not automatically make an OPK unusable. However, the evidence reviewed does not establish an accuracy percentage specifically for people with endometriosis.
Does a positive OPK mean endometriosis is not affecting fertility?
No. A positive OPK detects an LH rise; it cannot show whether endometriosis is affecting fertility. It does not confirm egg release or establish egg quality, tubal function or the chance of pregnancy. A fertility assessment may consider other factors, including sperm, rather than treating a positive strip as a complete fertility check.
When should I seek fertility advice with endometriosis?
Speak with your GP or treating specialist when pregnancy becomes a priority. Known or suspected endometriosis is a reason to discuss assessment earlier rather than automatically waiting 12 months. You do not need months of ovulation-test records before making that appointment.
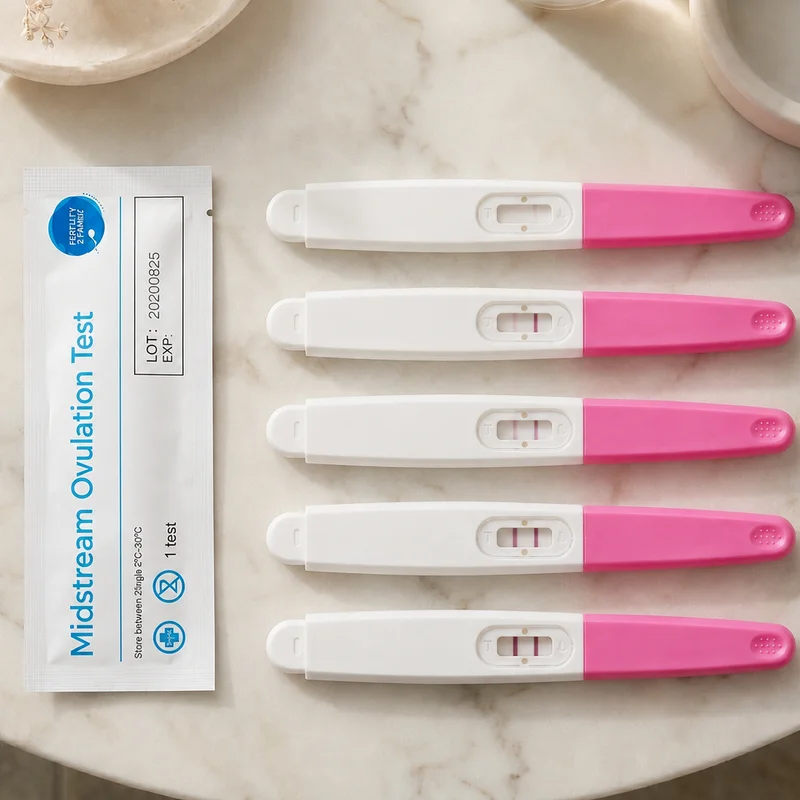
What can an ovulation test tell you about endometriosis?
Most OPKs detect whether LH has reached the test’s positive threshold. They do not give a laboratory blood LH value. A surge commonly comes before ovulation by about a day or two, but the interval varies and an LH rise is not always followed by egg release.
Many people with endometriosis still ovulate and conceive naturally. Endometriosis can nevertheless involve inflammation, scarring and ovarian cysts called endometriomas. Detecting LH cannot assess these changes or establish whether the fallopian tubes are functioning normally.
This is also why a manufacturer’s accuracy claim needs context. Detecting a hormone under test conditions is different from confirming ovulation, and neither is a prediction that pregnancy will follow. There is no established endometriosis-specific OPK accuracy figure in the guidance and research reviewed here.
A Cochrane review found that urine-test-guided intercourse probably improved pregnancy and live-birth outcomes in women under 40 who had been trying for less than 12 months. That finding does not establish an endometriosis treatment effect. Several included studies had manufacturer funding, and important uncertainties remained.
Does home ovulation tracking fit your endometriosis treatment?
During a natural cycle, an OPK may help you choose days for intercourse. During treatment designed to suppress ovulation, repeated testing may offer little useful information. In a monitored fertility cycle, your clinic’s instructions take priority over a home result.
Can hormonal endometriosis treatment affect ovulation testing?
Some endometriosis medicines suppress ovulation; others change bleeding without consistently stopping ovarian activity. A hormonal intrauterine device (IUD), for example, may make periods lighter or absent while ovulation continues. Bleeding changes during treatment therefore cannot tell you whether a natural-cycle testing schedule is appropriate.
Do not stop prescribed treatment to obtain an OPK result. Discuss a conception plan with your treating clinician, including symptom control while trying. Hormonal suppression is used for symptom management, not to improve unassisted conception while you are taking it.
Can fertility medicines or trigger injections affect an OPK?
Medicines containing LH or human chorionic gonadotrophin (hCG) can mislead some ovulation tests. If you have used a trigger injection or are having monitored treatment, follow the clinic’s blood-test, scan and timing schedule. Do not change medicine doses or procedure timing because an OPK looks different from expected.
What if you have endometriosis with PMOS or irregular periods?
Endometriosis and PCOS are different conditions, but they can coexist. PCOS is now called polyendocrine metabolic ovarian syndrome (PMOS). Some people with this condition have persistently higher baseline LH, which can make repeated positive OPKs difficult to interpret.
Our guide to ovulation tracking with PCOS/PMOS covers that separate problem. Very irregular periods or prolonged positive results should not automatically be attributed to endometriosis.
How should you track ovulation with endometriosis this cycle?
Start with the directions for the exact device in your hand. Tests can differ in their starting-day chart, sample timing and reading window. An app’s predicted ovulation day is an estimate, not a reason to disregard those directions.
- Choose the starting day from your cycle history. Count cycle day one from the first day of full menstrual flow. Use the device’s chart; variable cycles may require starting earlier rather than relying on an average.
- Prepare a valid sample. Check the expiry date and pouch. Follow the collection and fluid guidance for your test rather than applying a pregnancy-test rule.
- Time the reading. Check the control and interpret the result only inside the specified window. Drying changes do not create a new valid result.
- Record briefly, then act on the result. Note the date, cycle day and result. Once a clear surge is detected in a natural cycle, chasing a darker line usually adds little.
For Fertility2Family strips, the current ovulation test instructions use day 11 as the starting point for a 28-day cycle. Dip for five seconds without crossing MAX, lay the strip flat and read between five and ten minutes. Ignore later changes. Follow the leaflet supplied with your pack if it differs.
Fertility2Family strip instructions recommend testing between 10 am and 8 pm at a similar time each day, with reduced fluid intake for about two hours beforehand. Avoid deliberately dehydrating yourself.
These strip directions are not universal. Some digital devices have different urine-timing rules and must be read from their display, not from lines inside the stick. More expensive or more complicated testing does not automatically provide a better answer to an endometriosis-related fertility question.

What should you do with positive, negative or repeatedly positive OPKs?
First separate a valid result from an invalid or late reading. For Fertility2Family strips, a positive requires the test line to be at least as dark as the control. A lighter line is negative for the surge, even when two lines are visible.
| OPK result | What it can mean | What to do next |
|---|---|---|
| Clear positive | An LH rise was detected; ovulation may be approaching. | Use the result for timing in a natural cycle. It does not confirm egg release. |
| Faint line or negative result | The sample did not meet the device’s positive rule. You may be before or after the surge. | Continue within the recommended testing window; do not diagnose low LH from one strip. |
| No positive during the expected window | A brief or later surge may have been missed. Technique or a cycle without ovulation may also explain it. | Check starting day and sample method. Discuss recurring uncertainty, especially with irregular or absent periods. |
| Several positive days or repeated apparent surges | The pattern needs context, including baseline LH, medicines and the device’s interpretation rule. | Keep the dates and ask your clinician. Extra positive days do not mean repeated egg release. |
| No control, or a change noticed only after the time limit | The test is invalid or outside its reading window. | Use a fresh device as directed rather than re-reading the old one. |
A “false positive” can mean different things. A test may genuinely detect raised LH without ovulation being confirmed; medicines or another hormone condition can also complicate interpretation. A home test alone cannot distinguish these explanations.
Likewise, repeated negative ovulation tests deserve a review of the whole pattern, not an assumption that endometriosis has stopped ovulation. Troubleshooting should not postpone fertility advice when pregnancy is already a priority.
How should you use the fertile window with endometriosis?
The fertile window includes the five days before ovulation and ovulation day. It can begin before the first positive OPK, so intercourse only after a positive may miss earlier opportunities. Where comfortable and practical, intercourse every two to three days reduces the need to pinpoint ovulation.
After a clear positive in a natural cycle, intercourse that day and the next is a practical approach, not a guarantee or an exact countdown. Our guide to when to have sex after an LH surge explains how to use that signal without waiting for the darkest line.
Pain changes what is workable. Do not force intercourse to match a test. Tell your GP or gynaecologist if penetration hurts or symptoms are limiting sex; pelvic floor assessment may help when muscle dysfunction is contributing. The separate guide to ovulation pain and endometriosis covers the symptom question. Pain itself does not prove that an egg was released.
What if cervical mucus, BBT and OPKs do not agree?
Different signs answer different questions. Clear, slippery cervical mucus can indicate approaching fertile days, while an OPK detects LH. Neither directly observes ovulation. With fertile cervical mucus but a negative OPK, the signs may simply have been noticed at different points in the cycle.
Basal body temperature (BBT) looks backwards for a sustained rise associated with the post-ovulation hormone pattern. Even an ovulatory cycle may not produce an obvious two-phase chart. An unclear chart does not diagnose anovulation, and BBT is not reliable clinical confirmation. The BBT charting guide explains recording technique; adding it is optional, not a requirement.
Which clinical test can confirm whether ovulation occurred?
A progesterone blood test can provide evidence of recent ovulation when timed appropriately. It is commonly arranged about a week before the expected next period, not automatically on cycle day 21. One result does not assess the quality of the entire luteal phase.
With unpredictable periods, ask your clinician how the sample should be timed and whether it is needed at all. The fertility hormone guide gives worked collection-date examples to discuss with your clinician.
Serial follicle-tracking ultrasound can follow follicle growth and changes around ovulation. That is a different investigation from one pelvic scan assessing possible endometriosis. Neither an app date nor one OPK should be used to overrule a monitored-cycle plan.
What if OPKs are positive but pregnancy is not happening?
Ovulation is only one part of conception. Endometriosis may affect pelvic anatomy or ovarian function, and semen factors may also be relevant. A clear LH surge does not settle those questions, but difficulty conceiving does not mean natural pregnancy is impossible.
A fertility assessment may consider cycle history, appropriate imaging, the fallopian tubes and semen analysis when relevant. Which tests are useful depends on your circumstances; everyone with endometriosis does not need an identical panel.
Where an endometrioma or previous ovarian surgery is relevant, discuss ovarian reserve and the benefits and risks of further surgery. Surgery can affect reserve, so more surgery is not an automatic next step after an unsuccessful cycle. A consultation can clarify the options without committing you to IVF.
An AMH result may inform reserve assessment and treatment planning, but it is not an egg-quality test or a stand-alone prediction of natural conception. Once timing is reasonably covered, investigating the remaining question is more useful than collecting ever more OPKs.
When should you arrange fertility assessment for endometriosis in Australia?
With known or suspected endometriosis, discuss fertility when pregnancy becomes a priority. Current Australian guidance supports fertility-specialist referral when fertility is the main goal. Do not wait to meet a generic 12-month threshold or complete a set number of tracking cycles first.
Mention irregular or absent periods, previous pelvic or ovarian surgery, known endometriomas, pain affecting intercourse and any relevant sperm or partner factors when booking. Your age and how long you have been trying still matter, alongside these other factors. The guide to when to see a fertility specialist explains the referral pathway.
If endometriosis is suspected but not diagnosed, pelvic ultrasound is often an early investigation. Transvaginal ultrasound may be offered when appropriate and acceptable. A normal scan does not exclude superficial endometriosis, and surgery is not the first diagnostic step for everyone.
Which symptoms should not wait for another home test?
Seek urgent assessment for new severe abdominal or pelvic pain, particularly with persistent vomiting, fever or feeling very unwell. If pregnancy is possible, significant one-sided pain, shoulder-tip pain, or pain with bleeding or dizziness also needs urgent assessment. Do not assume it is your usual endometriosis pain.
Go to an emergency department for severe symptoms. Call 000 for an ambulance with collapse, fainting, heavy bleeding, severe illness or a life-threatening emergency. An OPK result should not delay care.
Which ovulation test format is easiest to use consistently?
Strips use collected urine; midstream devices offer direct sampling; digital devices display a result. Choose based on clear instructions, ease of reading and your routine, rather than expecting a special endometriosis test. Compare our ovulation test formats only if home tracking is useful to your plan. Changing format cannot resolve a clinical question about ovulation or fertility.

Frequently asked questions about endometriosis and ovulation tests in Australia
Can an ovulation test detect or rule out endometriosis?
No. An OPK detects a urinary hormone signal, not endometriosis lesions. Neither a positive nor a negative result diagnoses the condition. Assessment depends on symptoms, medical history and appropriate investigations; even a normal ultrasound does not exclude superficial endometriosis.
Does endometriosis always cause high LH levels?
No. There is no single LH pattern that identifies endometriosis or measures its severity. Persistently positive OPKs need to be interpreted alongside cycle timing, medicines and other conditions. A urine-test line cannot be converted into a blood LH measurement.
Does a faint OPK line mean my LH is too low?
Not necessarily. It may simply mean that the urine sample has not met the device’s positive threshold. A faint line cannot diagnose low blood LH, poor egg quality or infertility. Check the instructions, the control result and where you are in the testing window.
Is a digital ovulation test better for endometriosis?
A digital display may make the result easier to read, but better accuracy specifically in people with endometriosis has not been established in the evidence reviewed. Follow that device’s display instructions. Lines inside a digital test stick should not be interpreted as a separate result.
Do positive OPKs after endometriosis surgery mean my fertility is restored?
No. An LH rise after surgery does not establish that every factor affecting conception has been corrected. Follow your surgeon’s recovery advice and agreed fertility plan. Age, ovarian involvement, previous treatment and other fertility factors remain relevant, even when a surge is easy to detect.
Can I use ovulation tests to avoid pregnancy if I have endometriosis?
No. OPKs are not reliable contraception, and endometriosis does not mean you cannot become pregnant. A negative result does not identify a guaranteed safe day for unprotected sex. Ask your clinician about contraception when pregnancy is not your current goal.
Next Steps in Australia
Bring a concise record to your appointment: period start dates, the dates of valid OPK results, current medicines, symptoms affecting daily life or sex, and any previous imaging or operation reports. A note on your phone is sufficient; you do not need a perfect chart.
Ask: “Are we trying to improve timing, confirm ovulation or investigate another fertility factor?” Agree on what happens next and when to review the plan. If you are comparing services, our guide to choosing a fertility specialist in Australia helps you prepare questions about care and communication.
Keep testing only while the result makes a difference to what you do next. With endometriosis, a manageable tracking routine and an individual care plan are more valuable than repeatedly proving that an LH line can turn positive.
Last reviewed: 9 September 2026
Next scheduled review: September 2027
References
Fertility2Family articles are researched using Australian Government health guidance, professional clinical recommendations and peer-reviewed medical literature. The references below were used to research and medically review this article and provide additional reading for readers who want to explore the evidence in more detail.
Royal Australian and New Zealand College of Obstetricians and Gynaecologists Australian Living Evidence Guideline: Endometriosis
Current Australian living guideline covering endometriosis diagnosis, first-line imaging, treatment and fertility priorities, including fertility-specialist referral when fertility is a priority and why hormonal suppression does not improve unassisted pregnancy rates.
Pregnancy, Birth and Baby How endometriosis affects fertility and pregnancy
Australian consumer information explaining endometriosis, pelvic inflammation, adhesions and ovarian cysts, while recognising that many affected people conceive naturally and benefit from individual fertility advice.
Pregnancy, Birth and Baby Ovulation and fertility
Australian guidance on the fertile window, urinary LH testing, cervical mucus and progesterone blood testing, including earlier medical advice for people with endometriosis or other fertility concerns.
Your Fertility Right Time For Sex , When Do You Ovulate ?
Australian fertility education describing fertile days, cycle records and intercourse timing, including a regular intercourse approach when identifying the precise ovulation day is difficult.
Fertility2Family Ovulation Test Strip Instructions
Current Fertility2Family strip instructions covering cycle-based starting days, urine collection between 10 am and 8 pm, five-second dipping, five-to-ten-minute reading, control validity and positive, negative and invalid results.
American Society for Reproductive Medicine Fertility evaluation of infertile women: a committee opinion (2021)
Professional guidance on fertility assessment, urinary LH limitations, individualised progesterone timing, ultrasound and ovarian reserve testing, distinguishing evidence of ovulation from an assessment of overall reproductive potential.
Monash University PCOS Guideline/ PMOS Guideline
Australian-led guideline hub documenting the change from PCOS to polyendocrine metabolic ovarian syndrome and providing evidence-based resources for understanding the condition and its management.
Australian Journal of General Practice Endometriosis: A review of recent evidence and guidelines
Australian clinical review of endometriosis assessment, multidisciplinary care and fertility, including pelvic floor support and the need to balance endometrioma surgery against possible ovarian reserve effects.
Cochrane Database of Systematic Reviews Timed intercourse for couples trying to conceive
Systematic review evaluating ovulation-guided intercourse and pregnancy outcomes, with population-specific findings and important limitations involving study funding, uncertainty and applicability beyond the people studied.
Healthdirect Australia Intrauterine contraceptive device (IUD)
Australian consumer guidance explaining hormonal IUD effects on the uterine lining, bleeding and ovulation, helping separate absent periods during treatment from evidence about ovarian activity.
Clearblue Australia Frequently asked questions – Digital Ovulation Tests
Manufacturer guidance on digital ovulation testing and circumstances that can mislead results, including pregnancy, PCOS and fertility medicines containing LH or hCG.
Healthdirect Australia Abdominal pain
Australian guidance distinguishing recurrent abdominal pain needing medical review from severe pain, persistent vomiting, fever or serious illness requiring urgent assessment or emergency care.
Healthdirect Australia Ectopic pregnancy
Australian guidance describing ectopic pregnancy warning signs and assessment, including abdominal or shoulder-tip pain, bleeding, dizziness and fainting when pregnancy is possible.
Clearblue Australia Ovulation Test Digital
Current manufacturer instructions illustrating digital LH testing, device-specific collection rules and the requirement to interpret the display rather than lines inside the test stick.
American Society for Reproductive Medicine Am I Ovulating?
Patient education explaining urinary LH testing, progesterone assessment and ultrasound monitoring, including missed surges and why a detected LH rise is not conclusive evidence of egg release.