


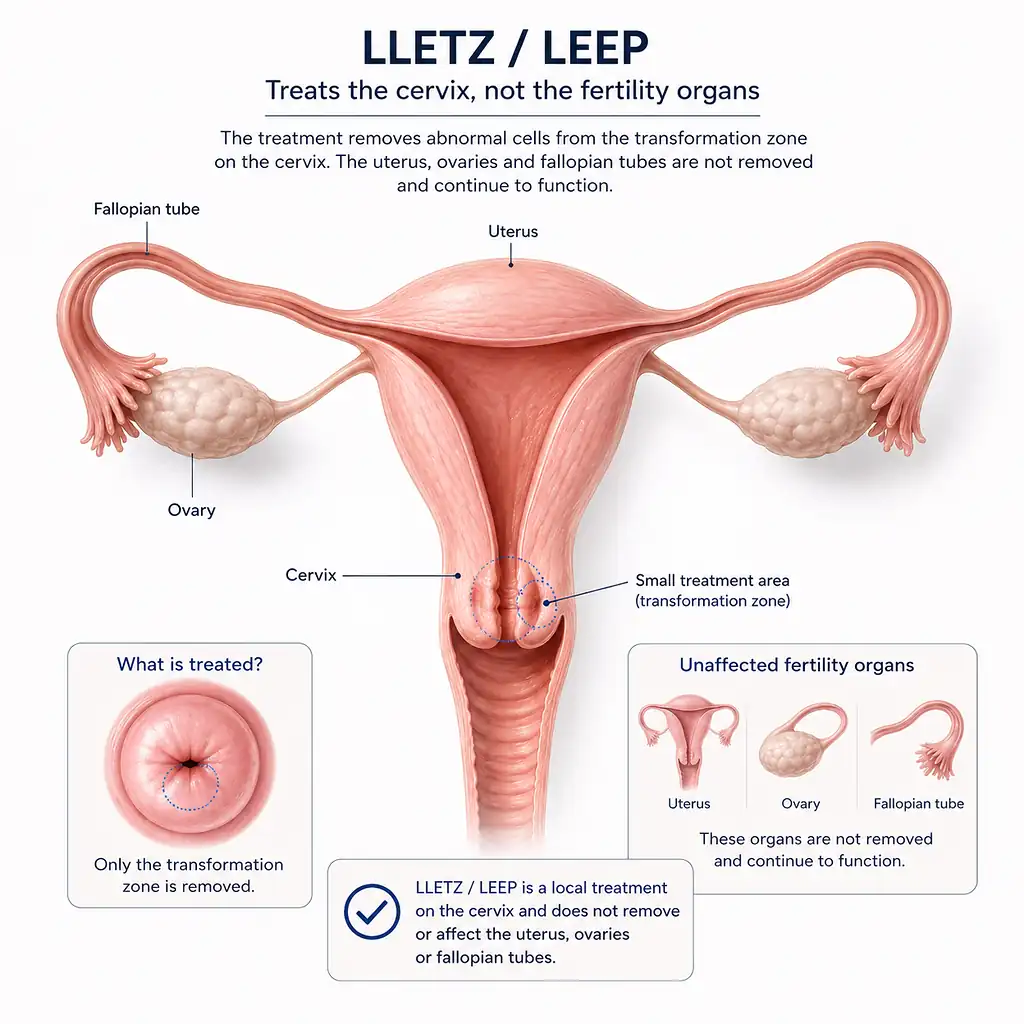
Being told you need a LLETZ or LEEP can make future pregnancy feel uncertain, even when the treatment itself was straightforward. The reassuring answer is that pregnancy is usually still possible because the treatment removes abnormal tissue from the cervix rather than the ovaries or fallopian tubes.
The harder question is when to start trying. Australian hospital instructions do not all use the same recovery period. Many advise avoiding vaginal intercourse for about three or four weeks, while some services recommend longer, so the discharge advice from the service that treated you matters more than one universal number.
Once healing, pathology and follow-up are clear, many people can move forward without fertility problems. If you later become pregnant, tell your GP, midwife or obstetric team about the treatment because the depth of excision and any repeat procedures can affect whether extra pregnancy monitoring is useful.
Quick answers about pregnancy after LLETZ or LEEP
Can you get pregnant after a LEEP procedure?
Yes. Pregnancy after LLETZ or LEEP is usually possible because the treatment removes abnormal tissue from the cervix rather than the ovaries or fallopian tubes. It does not usually stop ovulation or conception.
How soon can you get pregnant after a LEEP procedure?
Pregnancy can occur once ovulation and unprotected intercourse resume, but you should not start trying before your treating service says vaginal intercourse can resume. Australian hospital instructions commonly use about three or four weeks, while some services recommend longer.
Does LEEP affect fertility or future pregnancy?
Fertility is usually preserved. Cervical stenosis can occasionally affect sperm passage, while deeper or repeated cervical excisions are more relevant to later pregnancy monitoring and preterm-birth risk.

What LLETZ and LEEP mean in Australia
LLETZ means large loop excision of the transformation zone. It is the term commonly used in Australian hospitals and cervical-screening services. LEEP means loop electrosurgical excision procedure and is common in overseas information as well as Australian search queries. In this article, both terms refer to loop excision of abnormal cervical tissue.
Treatment is usually performed after cervical screening and colposcopy have identified an area that needs removal. The tissue goes to pathology so the treating team can confirm what was found, whether the edges of the specimen need discussion and what surveillance is required next.
A colposcopy with a small biopsy is not the same as an excisional procedure. If your paperwork only says colposcopy, ask whether tissue was sampled or whether a LLETZ, LEEP or cone biopsy was performed. Those details matter more for future pregnancy than the word colposcopy alone.
How soon can you try to get pregnant after LLETZ or LEEP?
Start by separating two questions: when can vaginal intercourse resume, and when is it appropriate to actively try for pregnancy?
Australian hospital instructions commonly restrict vaginal intercourse, tampons and other internal products for about three or four weeks after treatment, while some services recommend a longer period. The difference reflects local aftercare protocols and individual recovery, so follow the timeframe on your own discharge instructions.
Being cleared for intercourse is not always the only checkpoint. Before trying, you should know the pathology result, whether further treatment is being considered and when post-treatment cervical follow-up is due. A fixed waiting period from an overseas website should not replace advice from the clinician who knows your procedure and result.
The absence of bleeding does not prove that healing is complete. If discharge becomes offensive, bleeding is heavier than expected, fever develops or pelvic pain is worsening, contact the treating service or a GP before resuming intercourse.
What should be clear before you start trying?
Ask for the exact procedure name, pathology result, margin information if it was reported, next cervical follow-up date and whether another treatment is being considered. It is also reasonable to ask separately when vaginal intercourse can resume and when your treating team is comfortable with pregnancy attempts beginning.
Keep a copy of the treatment report. The number of procedures and the excision depth, when documented, can be more useful to the antenatal team than simply saying you once had abnormal cervical cells.
Can LLETZ or LEEP cause infertility?
Usually not. LLETZ or LEEP does not remove eggs, damage the fallopian tubes or switch off ovulation. The treatment is at the cervix, so most people retain the ability to conceive.
Cervical stenosis is a recognised complication in which scar tissue narrows the cervical opening. Estimates vary between studies and patient groups, and the practical fertility question is whether narrowing actually affects menstrual flow, cervical sampling or sperm passage. Risk is higher after repeated treatment or removal of a larger area of cervical tissue.
If periods become much lighter or more painful after treatment, cervical sampling becomes difficult, or conception is delayed, ask for assessment rather than assuming the cervix is the cause. Age, semen factors, ovulation, tubal health, endometriosis and time spent trying remain important parts of an Australian fertility assessment.
Pregnancy risks after LLETZ or LEEP
For most people, previous cervical treatment will not determine how the pregnancy turns out. The reason it still belongs in your antenatal history is that excisional treatment is associated with a higher average risk of preterm birth, particularly after repeated procedures or removal of a larger amount of cervical tissue.
This is an association, not a prediction. Studies do not all estimate the same level of risk, and the evidence is mainly observational. Current research also shows that procedure characteristics matter, which is why one small tissue-preserving excision should not be treated as equivalent to several or deeper procedures.
A previous LLETZ does not mean miscarriage is expected. Current professional guidance gives more attention to later pregnancy loss and preterm birth after more substantial or repeated cervical excision than to predicting an early miscarriage from a history of LLETZ alone.
Will you need cervical-length scans?
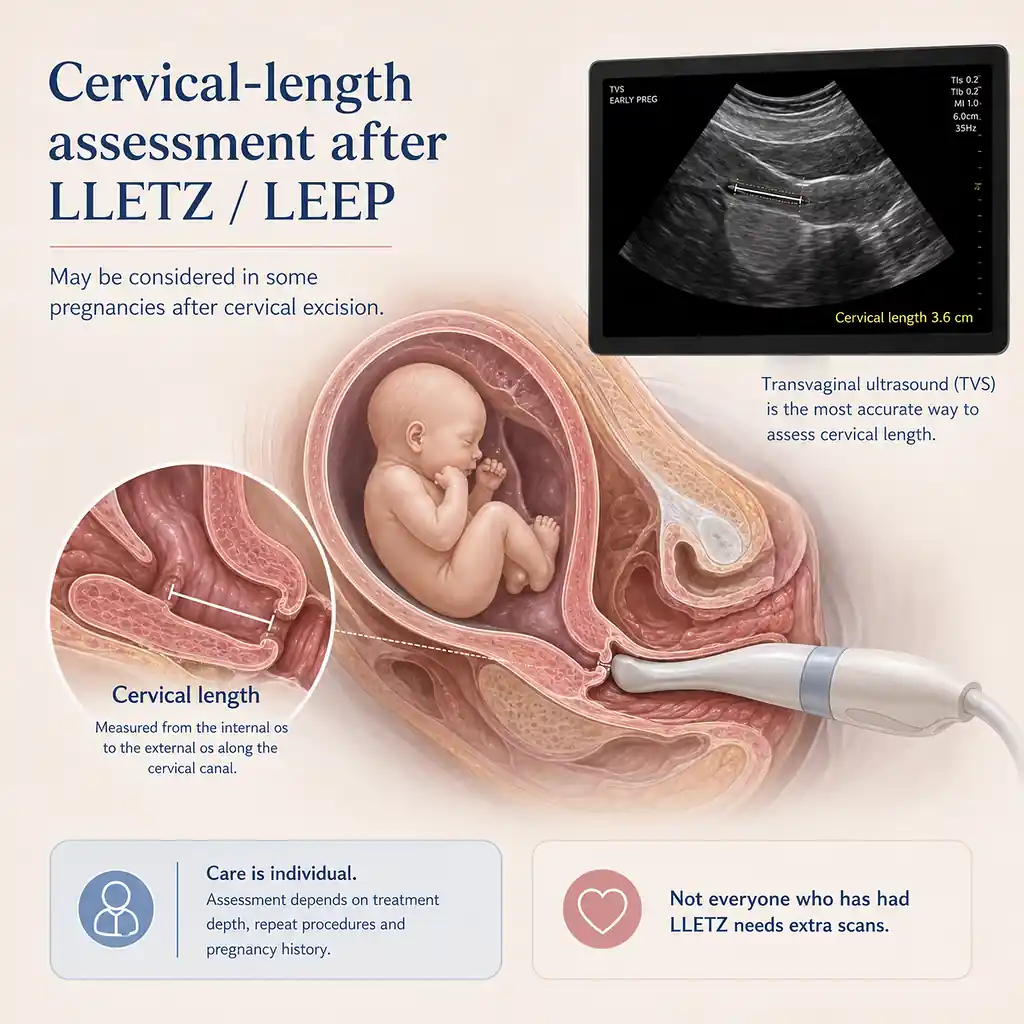
Not everyone needs the same monitoring. The decision can be influenced by the number and depth of treatments, a previous preterm birth or later pregnancy loss, and other findings in the current pregnancy.
If cervical length is assessed, transvaginal ultrasound gives the most accurate measurement. The result is interpreted with the rest of the pregnancy history rather than used as a stand-alone prediction of what will happen.
What if you become pregnant sooner than planned?
Contact your GP and the service that performed the LLETZ or LEEP. Becoming pregnant before the planned review does not automatically mean the pregnancy is unsafe. Healing, pathology and cervical follow-up simply need to be considered alongside routine pregnancy care.
A home pregnancy test cannot assess the cervix or show whether treatment follow-up is complete. After a positive result, the first steps after a positive pregnancy test can help you organise the GP or midwife appointment without using repeated home tests as a health check.
Cervical screening and follow-up during pregnancy
Do not let pregnancy quietly replace the follow-up that was planned after treatment. Tell the cervical-screening provider or colposcopy service that you are pregnant and that you previously had cervical treatment.
Australian guidance allows cervical screening and colposcopy during pregnancy when they are clinically indicated. The provider may adjust the timing or method according to the previous result, the reason for surveillance and the stage of pregnancy.
If you are already under follow-up for a previous abnormal result or treatment, do not assume a routine self-collected sample is the right test. Use the pathway recommended by the clinician managing your cervical history.
Tracking ovulation once you have been cleared to try
A previous LLETZ or LEEP does not change what a urinary LH test measures. Once your service says it is appropriate to try, ovulation testing can help identify the LH rise before ovulation, but it cannot confirm cervical healing or predict pregnancy outcome.
If repeated testing across several days suits your routine, ovulation test strips provide a lower-cost dip-and-read option for following the urinary LH pattern. If you prefer direct testing without collecting urine in a cup, midstream ovulation tests provide the same type of LH timing information in a different format.
Cervical mucus can be difficult to interpret while discharge is changing after treatment. Even after recovery, mucus is a fertile-window sign rather than proof of egg release. The explanation of fertile cervical mucus without confirmed ovulation can help when mucus and other cycle signs do not seem to agree.
If no clear positive LH result appears, testing may have started too late, a brief surge may have been missed or urine may have been diluted. The guide to what a missing LH surge can and cannot mean separates test timing from patterns that deserve medical review.
When should you see a GP or fertility specialist?
Book a GP appointment before trying if the pathology or follow-up plan is unclear, you have had more than one cervical excision, the procedure was described as deep, periods changed substantially after treatment, or another fertility concern is already present.
Australian guidance recommends fertility advice after 12 months of trying if you are 35 years or younger, or after 6 months if you are 36 years or older. Earlier review is reasonable when a known condition or treatment may affect fertility.
If your period is late, a negative result may simply be too early or the cycle may have shifted. The late period and negative pregnancy test pathway explains when repeating a test becomes useful and when to speak with a GP.

Frequently Asked Questions about pregnancy after LLETZ or LEEP in Australia
Can you get pregnant after LLETZ?
Yes. LLETZ does not usually prevent ovulation or conception. Most people can still plan a pregnancy, although your pathology result, healing and treatment history determine the advice that applies to you.
How long after LLETZ should you wait before trying?
Use the discharge advice from the service that performed your treatment. Australian hospital instructions commonly restrict vaginal intercourse for about three or four weeks, while some services recommend longer. Pregnancy attempts may also need to wait until pathology and follow-up are clear.
Can LEEP cause infertility?
Usually not. Cervical stenosis can occasionally narrow the cervical opening enough to affect menstrual flow, cervical sampling or sperm passage. If periods change substantially after treatment or conception is delayed, ask for assessment rather than assuming the cervix is the cause.
Does LLETZ increase miscarriage risk?
A previous LLETZ does not mean miscarriage is expected. Current professional guidance gives more attention to later pregnancy loss and preterm birth after larger or repeated cervical excisions than to predicting an early miscarriage from a history of LLETZ alone.
Will I need cervical-length scans after LLETZ?
Not everyone needs the same monitoring. The antenatal team considers the number and depth of cervical treatments, previous preterm birth or later pregnancy loss, and the rest of your pregnancy history before deciding whether cervical-length assessment is useful.
What if I got pregnant right after LEEP?
Contact your GP and the service that performed the procedure. They can review healing, pathology, cervical follow-up and routine pregnancy care without assuming that becoming pregnant sooner than planned means a poor outcome.
Next Steps in Australia
Read the discharge instructions from the service that performed the LLETZ or LEEP, attend the pathology or result appointment and ask when vaginal intercourse and pregnancy attempts can resume. Keep the procedure report with your cervical-screening records.
Arrange a GP preconception review when medicines, folic acid, iodine, vaccinations or other health conditions need checking. If pregnancy has already occurred, tell the GP or midwife about the cervical treatment at the first appointment and take the report with you.
Contact the treating service or a GP for heavy bleeding, fever, offensive discharge or worsening pelvic pain during recovery. Call 000 for a life-threatening emergency.
Last reviewed: 19 August 2026
Next scheduled review: August 2027
References
Fertility2Family articles are researched using Australian Government health guidance, professional clinical recommendations and peer-reviewed medical literature. The references below were used to research and medically review this article and provide additional reading for readers who want to explore the evidence in more detail.
You can read how we research, write and check our health information in our editorial and medical review policy, and see who reviews our articles and their clinical credentials.
Australian Government Department of Health, Disability and Ageing National Cervical Screening Program: Understanding the National Cervical Screening Program Management Pathway Current Australian national pathway for cervical screening, colposcopy, treatment of cervical abnormalities and post-treatment surveillance, including follow-up after excisional treatment.
Royal Hospital for Women, South Eastern Sydney Local Health District After your LLETZ Procedure New South Wales hospital aftercare for LLETZ covering cervical healing, vaginal restrictions, expected bleeding or discharge, pathology follow-up and symptoms that need medical review.
The Royal Women’s Hospital LEEP, LLETZ or cone biopsy procedure – going home after a local anaesthetic Victorian hospital guidance on recovery after LEEP, LLETZ or cone biopsy, including intercourse restrictions, bleeding, discharge, infection precautions and post-procedure care.
Cancer Council Australia Colposcopy Australian cancer information explaining colposcopy, biopsy and LLETZ as a common treatment for precancerous cervical cell changes.
Healthdirect Australia Colposcopy Australian consumer guidance on colposcopy, cervical biopsy, pregnancy considerations and warning symptoms such as fever, offensive discharge, severe pelvic pain or heavy bleeding.
Pregnancy, Birth and Baby Cervical screening during pregnancy Australian pregnancy guidance on cervical screening and colposcopy during pregnancy, including the need to discuss previous abnormal results and prior cervical treatment with the doctor or midwife.
Royal Australian and New Zealand College of Obstetricians and Gynaecologists Measurement of Cervical Length for Prediction of Preterm Birth (C-Obs 27) RANZCOG clinical guidance on cervical-length assessment, transvaginal ultrasound and preterm-birth risk after previous cervical excision, including the relevance of larger or repeated procedures.
HealthyWA Preterm birth prevention Western Australian public-health guidance listing prior cervical surgery such as cone biopsy or LLETZ as a preterm-birth risk factor and explaining when cervical-length ultrasound may be considered.
Healthdirect Australia Planning for your pregnancy Australian preconception guidance on GP review, medicines, supplements, ovulation tracking and when to seek fertility advice according to age, time trying and known reproductive concerns.
Pregnancy, Birth and Baby Infertility Australian guidance on delayed conception, when fertility assessment is recommended and why earlier review may be appropriate when a known condition or treatment could affect fertility.
Royal College of Obstetricians and Gynaecologists Large loop excision of the transformation zone (LLETZ) UK professional patient guidance on LLETZ recovery, cervical stenosis, future pregnancy and the greater relevance of repeated treatment or removal of a larger amount of cervical tissue.
Royal College of Obstetricians and Gynaecologists Cervical screening, colposcopy and pregnancy Current professional guidance explaining that most previous cervical treatment does not affect pregnancy, while excisional treatment can justify additional pregnancy assessment depending on the number of procedures and the amount of cervix removed.
The Lancet Oncology Comparative effectiveness and risk of preterm birth of local treatments for cervical intraepithelial neoplasia and stage IA1 cervical cancer: a systematic review and network meta-analysis A 2022 systematic review and network meta-analysis comparing LLETZ with other cervical treatments, showing that reproductive risk varies by treatment type and that the preterm-birth evidence is largely observational.
Journal of Maternal-Fetal & Neonatal Medicine Association between loop electrosurgical excision procedure and adverse pregnancy outcomes: a meta-analysis A 2023 meta-analysis of 30 studies examining associations between previous LEEP and later pregnancy outcomes including preterm delivery, prelabour membrane rupture and low birth weight.
Archives of Gynecology and Obstetrics Pregnancy outcome and risk of recurrence after tissue-preserving loop electrosurgical excision procedure (LEEP) A 2023 cohort study of tissue-preserving LEEP that found no clear increase in prematurity or miscarriage in that cohort, supporting the importance of procedure characteristics rather than treating every excision as equivalent.
Archives of Gynecology and Obstetrics Uterine cervical stenosis: from classification to advances in management. Overcoming the obstacles to access the uterine cavity A 2024 review of cervical stenosis, its variable definitions and clinical consequences, supporting cautious interpretation of scar-related narrowing rather than applying one incidence figure to every person after cervical treatment.