


Seeing a positive ovulation test on day 8, 10 or 11 can make you wonder whether your cycle has gone wrong or whether you have missed your best chance to conceive. Earlier ovulation can be normal in a shorter cycle. It does not, by itself, prove poor egg quality, low ovarian reserve or infertility.
The practical issue is timing. If the fertile window opens earlier, waiting for a predicted day 14 can mean starting LH testing or intercourse too late. A one-off earlier result often matters less than a new pattern that repeats.
A new or repeated change deserves more attention than one unusual month. Medical review is also appropriate when bleeding changes, cycles repeatedly fall outside the usual range or fertility assessment is due.
Quick answers about early ovulation
What causes ovulation to happen earlier than expected?
An earlier ovulation date can reflect a naturally shorter follicular phase, ordinary cycle variation, an inaccurate app prediction, a changing cycle after childbirth or hormonal contraception, perimenopause, or a fertility-treatment cycle. One early result does not identify the cause by itself.
How can you tell whether ovulation was actually early?
An app predicts timing. Cervical mucus can show that the fertile window is opening, a urine ovulation test detects the LH rise before likely ovulation, and basal body temperature rises afterwards. Combining these clues gives a stronger estimate, but home tracking cannot confirm the exact moment of egg release.
When should you see a GP about early ovulation?
Book a GP appointment if earlier timing repeats with very short or irregular cycles, the change is new or persistent, bleeding is unusual, or you have reached the usual fertility-assessment timeframe. Seek earlier advice if you have a known reproductive or hormonal condition or are in fertility treatment.

What does early ovulation mean?
Cycle day 1 is the first day of full menstrual flow. Ovulation ends the follicular phase, so an earlier date means this first part of the cycle was shorter than expected.
Day 14 is a familiar example because it sits near the middle of a typical 28-day cycle. It is not a pass-or-fail rule. Large cycle studies show that the follicular phase varies more than the luteal phase, so different cycle lengths often reflect different ovulation days.
A 2026 prospective study followed 1,051 women who each contributed 12 cycles. Ovulation timing shifted by at least four days in 96.5% of participants and by at least a week in 54.8%. The study does not define what is normal for every individual, but it shows why one app date should not be treated as fixed biology.
The useful comparison is your repeated pattern. An earlier date mainly shifts the fertile window, which begins before ovulation because sperm can survive in the reproductive tract for several days.
What causes early ovulation?
Early ovulation can reflect a stable shorter cycle rather than a medical problem. A person whose cycles usually last in the low twenties may have a shorter follicular phase and ovulate earlier than someone whose cycles usually last around 30 days.
The result may also be a prediction error. Calendar apps use previous averages and cannot see the current cycle’s cervical mucus, LH rise, temperature shift or follicle. An app can therefore label normal variation as early ovulation.
Cycle timing can be less predictable after childbirth, after a change in hormonal contraception and during perimenopause. Fertility medicines and monitored treatment cycles can also change expected timing. In a treatment cycle, use the clinic’s instructions rather than a general calendar rule.
Why did I ovulate early this month?
When one cycle appears earlier than usual, ordinary variation or an inaccurate prediction may be more plausible than a new diagnosis. Illness, stress, travel, disrupted sleep or a major routine change can coincide with altered cycle regularity, but the direction is not predictable and one result cannot prove the cause.
Compare two or three cycles before drawing a firm conclusion, unless the change comes with unusual bleeding, persistent pain, fertility treatment or another symptom that needs earlier assessment.

How early can you ovulate, and are days 8, 10 or 11 too early?
There is no clinically useful universal earliest normal ovulation day that can be read from a home test alone. Cycle length, bleeding duration, the evidence used to estimate ovulation and the interval before the next period all change the interpretation.
Ovulation on day 10 or 11 can fit a cycle in the low twenties. Ovulation estimated on day 8 or 9 deserves a careful check of cycle day 1 and the tracking method, but the date is not automatically abnormal. A positive LH test can precede egg release by a variable interval, so a positive result on day 8 does not prove ovulation occurred on day 8.
Ovulation can also appear close to the end of a period when bleeding lasts several days and the follicular phase is short. This is one reason intercourse during or soon after a period can overlap an early fertile window.
Treat the date as a range when the evidence is uncertain. A cycle supported by cervical mucus, an LH rise and a later temperature shift is more informative than an app prediction alone.
What are the signs of early ovulation, and how can you confirm timing?
Early ovulation symptoms are the same fertile signs that can appear later in another cycle. Cervical mucus may become wetter, clearer, slippery or stretchy. Some people notice a brief pelvic twinge, breast tenderness or increased sex drive, but symptoms alone are not reliable enough to date ovulation.
A urine ovulation test detects a rise in luteinising hormone. A faint ovulation-test line is usually not positive unless it meets the comparison rule for that device. A clear positive predicts likely ovulation but does not confirm egg release or the exact hour.
Basal body temperature works in the opposite direction because the sustained rise appears after ovulation. A consistent basal body temperature chart can add retrospective support, although sleep, illness, alcohol and measurement timing can affect individual readings.
If appropriately timed testing repeatedly shows no clear LH surge, the question is different from confirmed early ovulation. A missed short surge, later ovulation or an anovulatory cycle may need to be considered.
Clinical monitoring can answer a different question. A clinician may use ultrasound or appropriately timed progesterone testing when confirmation would change care, while interpreting the result with the wider cycle history.
Early ovulation decision guide
Use the pattern below to decide whether the next step is earlier tracking, another cycle of observation or a GP review.
| What you have noticed | What it can tell you | Useful next step |
|---|---|---|
| An app predicts an earlier day, without other signs | This is a forecast rather than evidence that ovulation occurred. | Begin observed tracking earlier and keep the prediction provisional. |
| One early LH rise or fertile-mucus change in a cycle lasting 21 to 35 days | This may be ordinary variation or your normal shorter pattern. | Cover the fertile window and record when the next full period begins. |
| Earlier timing repeats and the whole cycle is shorter than 21 days | The repeated pattern needs clinical context rather than a home diagnosis. | Take two or three cycles of records to a GP. |
| Tests conflict, bleeding is unusual or you are in fertility treatment | General calendar rules are not enough to interpret the cycle safely. | Follow the advice of your GP or fertility clinic. |
How does early ovulation change the fertile window?
The main effect is an earlier start to the days when conception is possible. Sperm can survive for up to five days, while the egg has a much shorter lifespan after release. Intercourse before ovulation therefore matters as much as intercourse on the estimated ovulation day.
Having intercourse every two to three days in the week before and around expected ovulation can cover the window without requiring one perfect test. After a clear positive result, timing intercourse after an LH surge can include the positive-test day and the following day when practical.
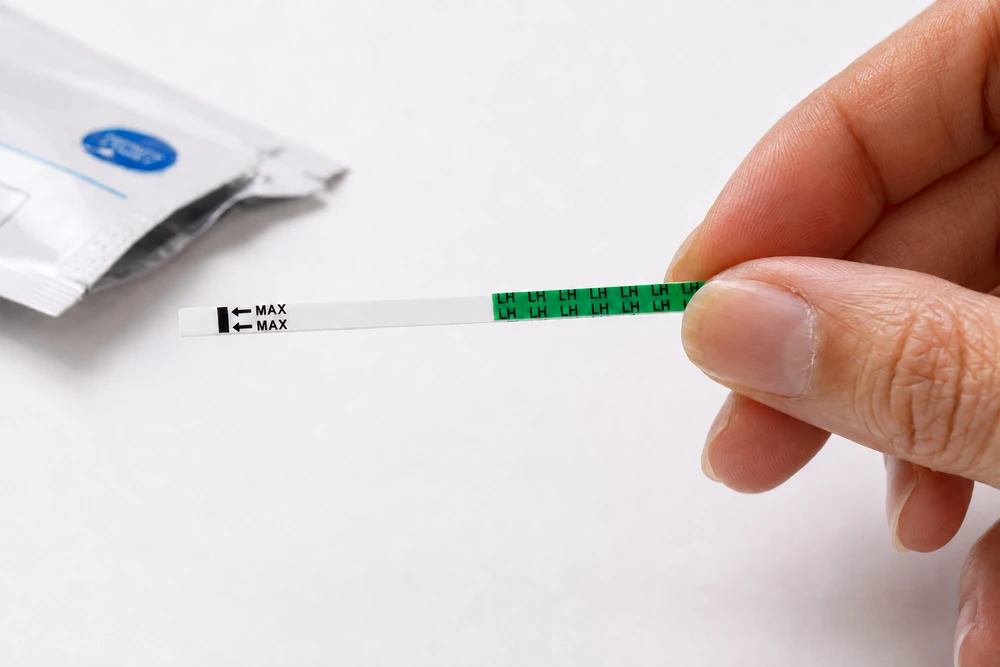
If you need to begin testing earlier or continue across more days, dip-strip ovulation tests can suit repeated testing, while midstream tests suit people who prefer direct use without collecting urine. Fertility2Family sells home ovulation tests. Both formats detect urinary LH and cannot confirm egg release, egg quality or pregnancy.
Can you get pregnant if you ovulate early?
Yes. Pregnancy can occur after early ovulation when intercourse covers the fertile window and the other factors needed for conception are favourable. Earlier timing does not make a cycle infertile by definition.
A prospective study of 696 cycles found no evidence that ovulation before day 13 made a cycle inherently less fertile. That finding does not rule out an individual problem when cycles are repeatedly very short, but it challenges the idea that an earlier date automatically means an immature egg or failed conception.
The practical disadvantage is easier to understand: if ovulation arrives before you expect it, intercourse or testing may begin after the most fertile days have passed.
Does early ovulation mean poor egg quality or low ovarian reserve?
No. Cycle day and ovulation-test darkness do not measure egg quality. Ovarian reserve mainly describes the number of eggs remaining, while egg quality is a different concept that is strongly related to age.
Reproductive ageing can be associated with shorter cycles and a shorter follicular phase at a population level. That association does not mean every early cycle signals low reserve, and one OPK result cannot diagnose diminished ovarian reserve.
Even formal ovarian reserve tests have limits. They are used mainly to help predict response to ovarian stimulation and must be interpreted with age, reproductive history and the clinical reason for testing.
Is a short follicular phase the same as a short luteal phase?
No. The follicular phase runs from cycle day 1 to ovulation. The luteal phase runs from ovulation to the next period. Early ovulation describes the first interval and does not determine the length of the second.
Calculate luteal phase length with one consistent convention and treat the answer as an estimate when ovulation timing is uncertain. If a well-supported interval repeatedly measures 10 days or less, discuss the pattern with a GP rather than diagnosing a progesterone problem from home tracking.
An early period while trying to conceive may reflect earlier ovulation, a different post-ovulation interval, uncertain dating or bleeding that was not a true period.
Can early ovulation be treated or prevented?
A stable shorter cycle does not necessarily need treatment. The first question is whether ovulation is genuinely earlier than your usual pattern and whether the total cycle, bleeding and post-ovulation interval are otherwise concerning.
An earlier date is not something to try to correct with hormones, fertility medicines, supplements or restrictive diets on your own. When a medical condition or fertility-treatment plan is involved, management targets that cause or treatment goal.
In a monitored cycle, the clinic’s testing and medicine schedule takes priority over general advice.
When should you see a GP about early ovulation in Australia?
Book a GP appointment if cycles repeatedly last fewer than 21 days or more than 35 days, the timing changes markedly and stays different, periods become very irregular, or the pattern is affecting attempts to conceive.
Seek assessment for very heavy or prolonged bleeding, bleeding between periods, bleeding after sex, persistent pelvic pain or other new symptoms. If you notice mid-cycle bleeding, record the timing and flow rather than assuming it confirms ovulation.
Healthdirect advises seeing a doctor after 12 months of trying if you are 35 years or younger, or after 6 months if you are 36 years or older. Earlier review can be appropriate with a known reproductive condition, very irregular cycles or fertility treatment.
A GP can review the cycle history and decide whether blood tests, ultrasound or referral are relevant. Seeing a fertility specialist in Australia may be the next step when initial assessment suggests specialist care or the usual trying timeframe has been reached.

Frequently Asked Questions about Early Ovulation in Australia
Is ovulation on day 10 or 11 too early?
Not necessarily. Day 10 or 11 can fit a shorter cycle, particularly when the pattern is consistent and there is a reasonable interval before the next period. Check how ovulation was estimated rather than treating the calendar day alone as abnormal.
Can ovulation happen on day 8 or right after your period?
It can be estimated that early, especially in a short cycle or after a longer period, but first confirm cycle day 1 and the evidence used to date ovulation. Because sperm can survive for several days, intercourse during or soon after a period can still fall within an early fertile window.
Does early ovulation cause infertility?
No. Earlier timing alone does not diagnose infertility. It may make the fertile window easier to miss, while repeated very short cycles or another reproductive concern can justify individual assessment.
Does early ovulation make your period come early?
It can. If the interval after ovulation stays similar, an earlier ovulation day may be followed by an earlier period. The interval also varies, and an uncertain ovulation estimate can make the relationship look more exact than it is.
Can stress make you ovulate early?
Stress can affect cycle regularity and can make sleep, temperature and other tracking signs harder to interpret. It does not shift ovulation in one predictable direction for everyone, so one early result cannot prove that stress was the cause.
Can an app accurately predict early ovulation?
Use an app as a record and a prompt for when to begin tracking, not as confirmation that ovulation occurred. When cycles vary, enter accurate period dates and begin observed tracking before the earliest recent forecast.
Next Steps in Australia
During the next cycle, mark the first day of full menstrual flow as cycle day 1, begin observing fertile signs before the earliest window you have seen, follow the instructions for one consistent test method and record when the next period begins.
Take the record to a GP if the earlier pattern repeats, cycles are consistently outside the usual range, bleeding is unusual or fertility assessment is due. Bring the first day of each period, the first clear positive LH result, any sustained temperature rise, bleeding changes, medicines and the date you began trying to conceive.
Last reviewed: 5 September 2026
Next scheduled review: September 2027
References
Fertility2Family articles are researched using Australian Government health guidance, professional clinical recommendations and peer-reviewed medical literature. The references below were used to research and medically review this article and provide additional reading for readers who want to explore the evidence in more detail.
Commercial disclosure: Fertility2Family sells home fertility tests. Product links are included only when they support a relevant reader decision and do not change the medical evidence, limitations or review standards applied to this article.
Pregnancy, Birth and Baby. Ovulation and fertility
Australian guidance on the fertile window, cervical mucus, basal body temperature, urinary LH testing, progesterone testing and when to seek medical advice while trying to conceive.
Pregnancy, Birth and Baby. Fertility tests and treatments
Australian guidance on common fertility investigations and treatments, including ovulation problems, hormone testing, ultrasound and cause-directed management through a GP or fertility specialist.
Healthdirect Australia. Fertility awareness (natural family planning)
Australian guidance comparing cervical-mucus, temperature and calendar methods, including circumstances that make home fertility tracking less reliable for conception timing or pregnancy prevention.
Healthdirect Australia. Irregular periods
Australian guidance on the usual 21 to 35-day cycle range, changing period patterns, record-keeping, possible causes and circumstances that should be assessed by a doctor.
Healthdirect Australia. Perimenopause
Australian guidance on shorter, longer or irregular cycles during perimenopause, associated symptoms and bleeding changes that should prompt medical review.
Healthdirect Australia. Planning for your pregnancy
Australian preconception guidance covering intercourse timing, cycle tracking and when to see a doctor after trying to conceive, based on age and individual concerns.
Better Health Channel. The menstrual cycle
Victorian public-health guidance explaining cycle-day counting and the menstrual, follicular, ovulation and luteal phases, with ovulation usually occurring before the next period rather than on one fixed day.
Human Reproduction. Variations in ovulation time and menstrual cycle characteristics: analysis of a prospective long-term cohort study
Prospective study of 1,051 women across 12 cycles showing substantial within-person variation in cycle length and ovulation timing, including four-day or greater timing changes in most participants.
npj Digital Medicine. Real-world menstrual cycle characteristics of more than 600,000 menstrual cycles
Large observational analysis of 612,613 app-recorded ovulatory cycles showing that cycle and follicular-phase length vary substantially and that longer cycles mainly reflect a longer follicular phase.
BMJ. The timing of the “fertile window” in the menstrual cycle: day specific estimates from a prospective study
Prospective study of 696 cycles in 221 pregnancy planners showing a broad, sometimes unpredictable fertile window and no evidence that ovulation before day 13 made a cycle inherently less fertile.
Human Reproduction Update. The LH surge and ovulation re-visited: a systematic review and meta-analysis and implications for true natural cycle frozen thawed embryo transfer
Systematic review and meta-analysis showing marked variation in definitions of the LH surge and a 22 to 56-hour interval from surge onset to ovulation.
American Society for Reproductive Medicine. Testing and interpreting measures of ovarian reserve: a committee opinion (2020)
Committee opinion distinguishing ovarian reserve from egg quality and explaining that reserve tests mainly predict ovarian stimulation response rather than natural fertility independently of age.
Fertility and Sterility. Diagnosis and treatment of luteal phase deficiency: a Committee Opinion
Current committee opinion defining luteal phase deficiency in association with a luteal phase of 10 days or less while emphasising diagnostic limits and uncertainty in natural cycles.