


Pain around ovulation can be difficult to dismiss when it returns every month, spreads into your back or rectum, or interrupts work, sleep or sex. Endometriosis can be associated with pelvic pain around ovulation, but timing alone cannot show that endometriosis, or ovulation itself, caused it. Mild one-sided discomfort that settles within a couple of days can fit ordinary ovulation pain. Recurrent, worsening or disabling pain needs a broader assessment.
The pattern matters more than a single cycle day. Pain with periods, sex, bowel movements or urination can strengthen the reason to investigate endometriosis. A sudden or rapidly worsening episode can signal a separate acute condition and should not be dismissed as a familiar cycle symptom.
Quick answers about endometriosis and ovulation pain
Can endometriosis cause painful ovulation?
Yes. Endometriosis is one possible explanation for recurring pain around ovulation, especially when there is severe period pain, pain with sex or bowel or bladder symptoms. It is not the only cause, and timing alone is not diagnostic.
Can an ovulation test confirm what is causing the pain?
No. A urine ovulation test detects a rise in luteinising hormone and helps estimate when ovulation may be approaching. It cannot prove that an egg was released, identify the structure causing pain or diagnose endometriosis.
When should ovulation pain be assessed urgently?
Call 000 or go to the nearest emergency department for sudden severe or rapidly worsening pelvic pain, especially with nausea or vomiting, heavy bleeding, marked dizziness or fainting, or when pregnancy is possible. Use 000 if you need an ambulance or cannot travel safely.


Endometriosis symptom diary
Pelvic pain appointment record
Check urgent features, symptom recurrence and functional impact before starting the full appointment record.
About 2 minutes
Check urgent features, symptom recurrence and functional impact before starting the full appointment record.
This check helps organise an appointment; it does not diagnose endometriosis or grade its severity. Pelvic pain has several possible causes, and a clinician may need an examination or investigations.
Is painful ovulation normal, or could it be endometriosis?
Pelvic pain during ovulation, often called mittelschmerz when it is brief and cyclical, may feel like pressure, a twinge, cramping or a sharper pain low in the abdomen. It is often felt on one side and may last from a few minutes to a couple of days. A mild episode that settles can be consistent with ovulation, but no pain pattern confirms that an egg was released.
Endometriosis is more likely to enter the discussion when pain keeps returning, affects normal activities or occurs within a wider pattern. Endometriosis cramps during ovulation can feel similar to ordinary mid-cycle cramping, so the surrounding symptoms matter. Relevant clues include severe period pain, deep pain during or after sex, pelvic pain outside the period, heavy or irregular bleeding, fatigue, difficulty conceiving, and pain with bowel movements or urination.
You do not need to wait until pain is unbearable. A recurring pattern that changes work, sleep, exercise, sex or toileting is useful clinical information and deserves to be taken seriously.
| Pattern | What it may fit | Next step |
|---|---|---|
| Mild, brief, one-sided discomfort that settles | Can be consistent with ordinary ovulation pain. | Monitor the pattern and arrange routine review if it changes. |
| Recurring pain that affects work, sleep, exercise or sex, especially with period, bowel or bladder symptoms | Endometriosis, adenomyosis, an ovarian cyst, pelvic-floor pain or another pelvic condition may be considered. | Book a GP assessment and discuss whether expert pelvic imaging is appropriate. |
| Pain that lasts more than three days, is becoming stronger or no longer follows the usual pattern | The episode is less typical of brief ovulation pain and needs another explanation. | Arrange medical review rather than waiting for repeated cycles. |
| Sudden severe one-sided pain with nausea or vomiting | Ovarian torsion, a cyst complication, appendicitis or another acute condition must be considered. | Call 000 or go to an emergency department straight away. |
| Pain with fever, unusual discharge, heavy bleeding, faintness or possible pregnancy | Pelvic infection, ectopic pregnancy, internal bleeding or another urgent cause may be present. | Seek urgent assessment. Call 000 if symptoms are severe, you need an ambulance or you cannot travel safely. |
Why can endometriosis pain be noticed around ovulation?
Endometriosis is a chronic inflammatory gynaecological condition involving tissue similar to the lining of the uterus outside the uterus. Its causes are not fully understood. The condition can involve the ovaries and form an endometrioma, and it may be associated with inflammation, scarring or adhesions within the pelvis.
There is not one proven mechanism behind every episode of endometriosis ovulation pain. A normal ovarian event may be felt more strongly in an already painful pelvis. An endometrioma, scar tissue, pelvic-floor muscle tension or pain referred from another structure can also contribute. Endometriosis pain during ovulation is a timing description, not a separate diagnosis. The phrase “flare around ovulation” describes when symptoms are noticed; it does not identify the tissue or process causing them.
Pain intensity also does not reveal how much endometriosis is present. Some people with limited disease have substantial pain, while others with more extensive disease report little pain. Treatment decisions therefore need to reflect symptoms, daily impact, examination, imaging and personal priorities rather than pain severity alone.
What do the location and timing of pain tell you?
One side, both sides or pain after ovulation
Brief one-sided pain can fit ordinary ovulation pain, but it is not specific. Ovarian cysts and torsion can also cause one-sided pain. Pain felt on both sides or centrally does not prove that both ovaries released an egg; pelvic muscles, the bowel, bladder and referred pain can all change where discomfort is perceived.
Pain can continue after the day you expected to ovulate. The date may have been estimated incorrectly, or the pain may have another cause. Duration does not confirm endometriosis, but pain that persists beyond a couple of days, keeps returning or affects daily life is a reason to seek assessment.
Back pain, nausea, rectal pressure and bladder symptoms
Australian endometriosis guidance recognises lower-back, bowel and urinary symptoms as part of the possible presentation. Some people describe constipation, diarrhoea, pain with bowel movements, rectal pressure, urinary pain, urgency or a feeling of bladder pressure. Nausea may accompany pain but is not a specific sign of endometriosis.
These symptoms can also arise from gastrointestinal, urinary, pelvic-floor or musculoskeletal conditions. Sudden severe pain with vomiting is a different pattern from mild cyclical nausea and needs urgent assessment. Bloating is similarly non-specific, so persistent or severe symptoms should be considered separately from ordinary bloating around ovulation.
Bleeding or discharge with mid-cycle pain
Light spotting can occur around ovulation, but it cannot confirm that ovulation caused the pain. Heavy bleeding, bleeding that keeps returning, unusual discharge or fever changes the differential diagnosis. Comparing the amount, timing and associated symptoms with common patterns of ovulation bleeding can help you describe the episode accurately to a clinician.
How should you track pain around ovulation?
An app or calendar predicts ovulation from previous cycle dates. Ovulation usually occurs about two weeks before the next period, not automatically on cycle day 14, and the exact timing can vary. A predicted day is useful for planning but cannot show what structure is causing pain.
Urine ovulation tests detect a rise in luteinising hormone, or LH, that generally occurs before ovulation. A positive result can narrow the likely timing, but it cannot prove egg release or diagnose endometriosis, a cyst or infection. If a urinary LH clue would make your symptom record more useful, ovulation tests can support timing. Use them for timing rather than diagnosis.
Hydration, test timing, a brief surge and irregular cycles can affect home results. Ovulation test accuracy in Australia also depends on following the directions for the exact device. A darker line is not a measure of pain severity, endometriosis severity or fertility.
Record the cycle day, pain location, duration, severity, bleeding, bowel or bladder symptoms, medicines used and the effect on normal activities. The pelvic-pain record above is a documentation aid only. It cannot diagnose ovulation, endometriosis or another cause.
How is suspected endometriosis assessed in Australia?
A GP or gynaecologist will usually start with the symptom pattern and its effect on your life. They may ask about periods, sex, bowel and bladder symptoms, bleeding, previous pelvic infection or surgery, fertility goals, medicines and whether pregnancy is possible. An abdominal and pelvic examination may be offered when appropriate, but a normal examination does not rule out endometriosis.
Pregnancy testing, urine testing, cervical or vaginal swabs, blood tests or other investigations may be used when the history raises another possible cause. This is why assessment should not begin with the assumption that every mid-cycle pain episode is endometriosis.
What can ultrasound and MRI show?
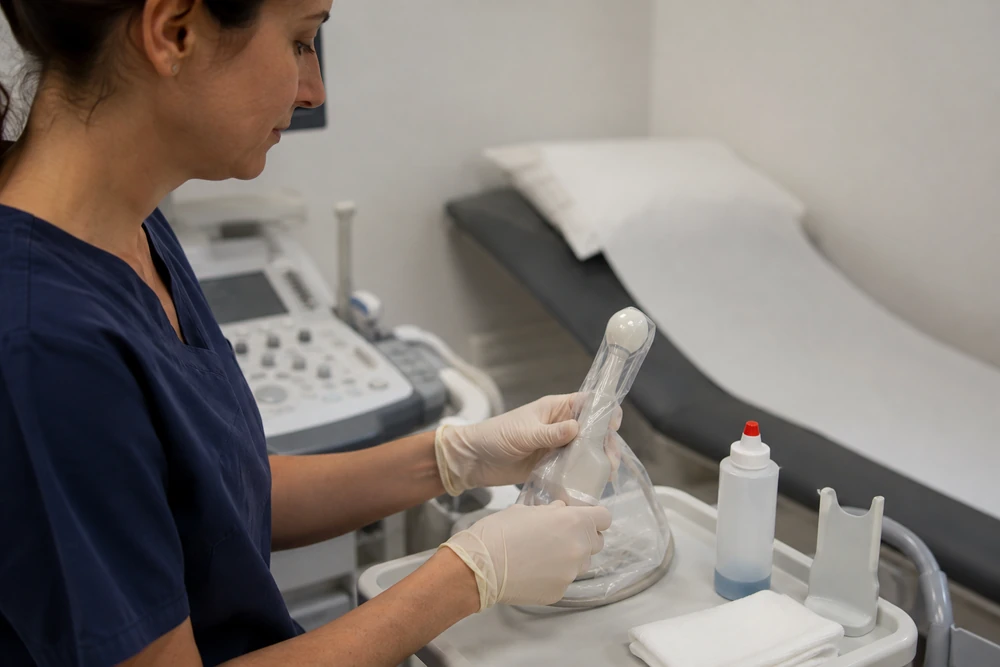
Australia’s living guideline recommends transvaginal pelvic ultrasound as the first-line investigation for symptoms suggestive of endometriosis. When an internal scan is not suitable, a transabdominal ultrasound may be considered. Specialist ultrasound and pelvic MRI should be performed or interpreted by clinicians with expertise in gynaecological imaging when that expertise is required.
MRI may be offered when ultrasound is unsuitable or when deep endometriosis is suspected. Expert imaging can identify ovarian endometriomas and many forms of deep disease, but negative ultrasound findings do not exclude superficial peritoneal endometriosis. Persistent symptoms still deserve review even when a scan is reported as normal.
When is laparoscopy considered?
Surgery is no longer required as the first step for diagnosis. Laparoscopy may be discussed when endometriosis remains suspected, symptoms have not improved with treatment, imaging is inconclusive, another condition needs investigation or surgery is being considered for treatment. The expected benefit, possible harms and effect on fertility planning should be explained before a decision is made.
Ask what each proposed test is intended to answer. A scan looking for an urgent cyst complication, an endometrioma, deep bowel or bladder disease, or information needed before surgery may require different expertise and preparation.
What can treatment look like when pain is the priority?
Endometriosis treatment is individual. Australian guidance supports shared decisions based on symptoms, treatment preferences, side effects, previous care and whether pregnancy is wanted now. Options may include appropriate pain relief, hormonal treatment, pelvic physiotherapy, psychological pain-management support and surgery in selected cases.
Hormonal treatments can reduce endometriosis-associated pain by changing or suppressing cyclical hormonal activity. They are not all interchangeable, and their suitability depends on medical history, side effects, contraception needs and pregnancy plans. A GP or gynaecologist can explain which option fits the goal of treatment.
For mild discomfort while you are waiting for review, rest, a warm bath or a heat pack may help. Ask a pharmacist or GP about medicines when pregnancy is possible or when you have other health conditions. Repeated self-treatment should not replace assessment when pain is persistent, worsening or disruptive.

What changes when pregnancy is a priority?
Does endometriosis stop ovulation?
Endometriosis does not automatically stop ovulation. A person may have regular cycles and still experience pain or fertility effects related to ovarian disease, pelvic anatomy or another factor. Irregular or absent periods need their own assessment rather than being attributed to endometriosis without evidence.
How does treatment change while trying to conceive?
Hormonal treatment used for endometriosis pain is not offered as a strategy to improve unassisted pregnancy rates while someone is actively trying to conceive. When fertility is a priority, pain management, imaging and conception planning should be considered together, and specialist input may be appropriate.
Painful ovulation does not predict who will conceive. A fertility assessment may consider age, cycle and ovulation history, the fallopian tubes, sperm, time trying, ovarian disease and previous surgery. The female fertility assessment pathway explains why no single symptom or diagnosis should carry the whole explanation.
Intercourse timing is a separate question from pain diagnosis. Understanding the fertile window can support conception timing, but neither a fertile-window estimate nor an LH result explains the source of pelvic pain.
When does pelvic pain need urgent care?
Severe ovulation pain should not be normalised simply because it recurs at mid-cycle. Call 000 or go to the nearest emergency department straight away for sudden severe or rapidly worsening pelvic or abdominal pain, especially when it is one-sided or occurs with nausea or vomiting. Emergency assessment is also important for heavy bleeding, marked dizziness, fainting, shoulder-tip pain, or severe pain when pregnancy is possible. Ovarian torsion, a ruptured or bleeding cyst, ectopic pregnancy, pelvic infection, appendicitis and other acute conditions can overlap with pain blamed on ovulation.
If you need an ambulance or cannot travel safely, call 000. A home pregnancy test cannot show where a pregnancy is located, so severe symptoms should be assessed on their own merits rather than waiting for a positive test.

Frequently Asked Questions about endometriosis and ovulation pain in Australia
How long can endometriosis ovulation pain last?
There is no fixed duration. Ordinary ovulation pain often lasts from minutes to a couple of days, while endometriosis-associated pelvic pain may persist or recur beyond mid-cycle. Pain lasting more than three days, worsening or disrupting daily life warrants medical review.
Can endometriosis pain continue after ovulation?
Yes. Pain may continue after the estimated ovulation day, but this does not show what caused it. Ovulation may also have occurred earlier or later than predicted. Persistent or recurrent pain needs assessment rather than a more precise calendar label.
Can endometriosis cause ovulation pain on both sides?
Pain can be felt on one side, both sides or centrally. The location does not prove which ovary released an egg or confirm endometriosis. Sudden severe one-sided pain with nausea or vomiting needs urgent assessment.
Can a normal ultrasound rule out endometriosis?
No. A negative result may make some forms of endometriosis less likely, but it cannot exclude superficial peritoneal disease. Ask whether the scan was designed and interpreted for suspected endometriosis, and seek review if symptoms persist.
Can nausea, back pain or rectal pressure happen around ovulation?
Yes, these symptoms can occur around ovulation and may be reported with endometriosis, but they are not diagnostic. Gastrointestinal, urinary, pelvic-floor and musculoskeletal causes can overlap. Sudden severe pain with vomiting requires urgent care.
Does painful ovulation mean I will have trouble getting pregnant?
No. Pain is not a fertility test, and many people with endometriosis conceive. When pregnancy is not occurring, assessment should consider age, ovulation, the fallopian tubes, sperm, time trying and any known pelvic disease.
Next Steps in Australia
If pain is mild, brief and settles, note when it occurred and watch for a change in duration, severity or associated symptoms. Book a GP appointment when it keeps returning, lasts longer than expected, affects daily activities or appears with painful periods, sex, bowel movements, urination or unusual bleeding.
Take your cycle record and any previous scan or surgery reports. Ask which causes are being considered, whether pregnancy or infection testing is relevant, what the proposed imaging can and cannot show, and whether a specialist endometriosis ultrasound or gynaecology referral would change care.
Australia now has a national Endometriosis Management Plan designed for use by patients and GPs. It can help structure conversations about symptoms, treatment goals, flare planning, referrals and ongoing review. Ask your GP whether using the plan would help organise your care.
If conception is a current goal, say so at the start because it changes the treatment discussion. When to see a fertility specialist in Australia outlines the referral factors to discuss with your GP when endometriosis, significant pelvic pain or another fertility concern is already present.
Last reviewed: 5 September 2026
Next scheduled review: September 2027
References
Fertility2Family articles are researched using Australian Government health guidance, professional clinical recommendations and peer-reviewed medical literature. The references below were used to research and medically review this article and provide additional reading for readers who want to explore the evidence in more detail.
Royal Australian and New Zealand College of Obstetricians and Gynaecologists (RANZCOG). Australian Living Evidence Guideline: Endometriosis
Current Australian living guideline covering assessment, first-line transvaginal ultrasound, MRI in selected cases, treatment choices, laparoscopy, pain management and fertility-priority referral.
Australian Institute of Health and Welfare. Endometriosis: What is endometriosis?
Australian Government overview describing endometriosis symptoms, including ovulation, pelvic, back, urinary and bowel pain, fertility effects, diagnosis and the weak relationship between symptom severity and disease extent.
Better Health Channel, Victorian Department of Health. Ovulation pain
Victorian public health guidance describing common ovulation-pain sensations and duration, alternative causes, self-care for mild symptoms and thresholds for medical assessment.
Pregnancy, Birth and Baby. Ovulation and fertility
Australian consumer guidance on ovulation timing, the fertile window and urinary LH testing, including the limits of home methods for predicting ovulation.
Healthdirect Australia. Ovarian torsion
Australian emergency guidance on sudden severe pelvic pain, nausea or vomiting, hospital assessment and the need for prompt treatment to protect ovarian function.
Healthdirect Australia. Ovarian cysts
Australian guidance on ovarian-cyst symptoms, endometriomas, ultrasound assessment and urgent warning signs such as sudden pelvic pain, nausea, heavy bleeding or faintness.
Healthdirect Australia. Ectopic pregnancy
Australian guidance on ectopic-pregnancy symptoms and emergency care, including pelvic or abdominal pain, bleeding, shoulder-tip pain, dizziness, faintness and ultrasound assessment.
STI Guidelines Australia. Pelvic inflammatory diseases (PID)
Australian clinical guidance describing pelvic inflammatory disease presentation, testing and prompt treatment, including pelvic pain, abnormal bleeding or discharge, fever, nausea and possible reproductive complications.
Healthdirect Australia. Infertility
Australian guidance on infertility causes and assessment, including age, ovulatory disorders, tubal factors, endometriosis and sperm-related factors, plus when earlier medical advice is appropriate.
Australian Government Department of Health, Disability and Ageing. New national tool to improve endometriosis care
Australian Government media release dated 2 September 2026 announcing the national Endometriosis Management Plan, developed by Monash University to support symptoms, treatment goals, referrals, flare planning and ongoing review.