

At 5 DPO, it can be hard to choose a testing date when cramps, discharge changes or having no symptoms keep drawing your attention back to pregnancy. A symptom can be real without being evidence of pregnancy. At an estimated five days past ovulation, symptoms cannot confirm implantation, and a home pregnancy test is usually too early to answer the question reliably.
The useful shift at 5 DPO is from decoding symptoms to making one sensible plan. This guide explains what the timing can and cannot show, then gives you one practical way to choose a later test date. For the wider day-by-day context, the two-week-wait decision map follows the period between ovulation and meaningful pregnancy testing.
Quick answers about 5 DPO symptoms
Can 5 DPO symptoms show whether you are pregnant?
No. Cramps, discharge changes, nausea, fatigue or no symptoms can all occur without identifying pregnancy. At an estimated 5 DPO, symptoms cannot confirm implantation or predict a later test result.
Is 5 DPO too early for a pregnancy test?
Usually, yes. Developing placental tissue starts producing hCG after implantation, and the hormone then needs to reach the detection level of the test used. A negative urine result at an estimated 5 DPO cannot rule pregnancy out.
What is the most useful next step at 5 DPO?
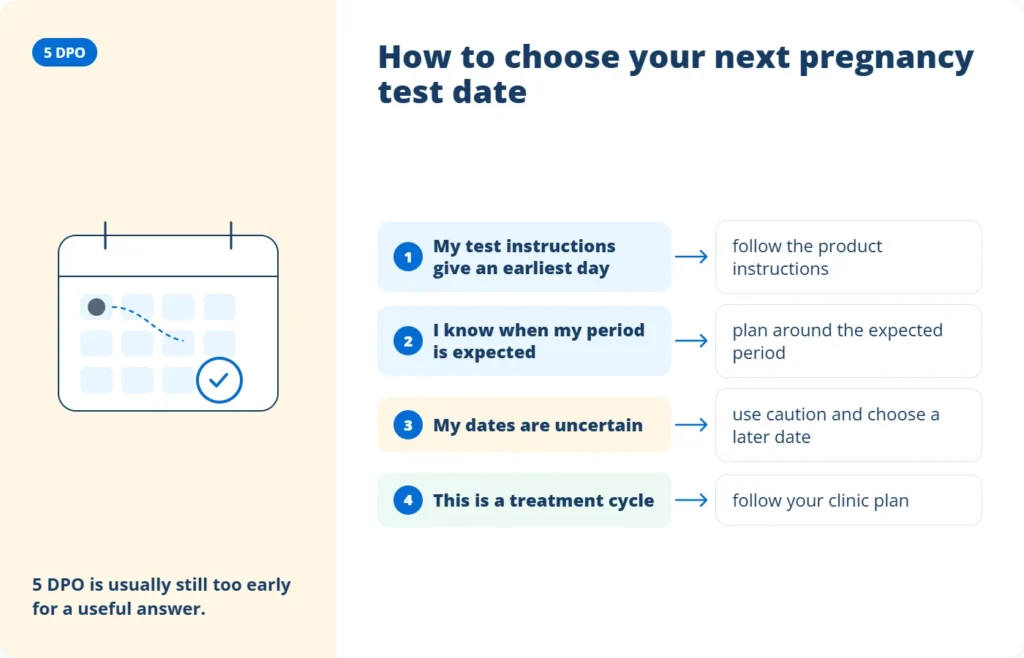
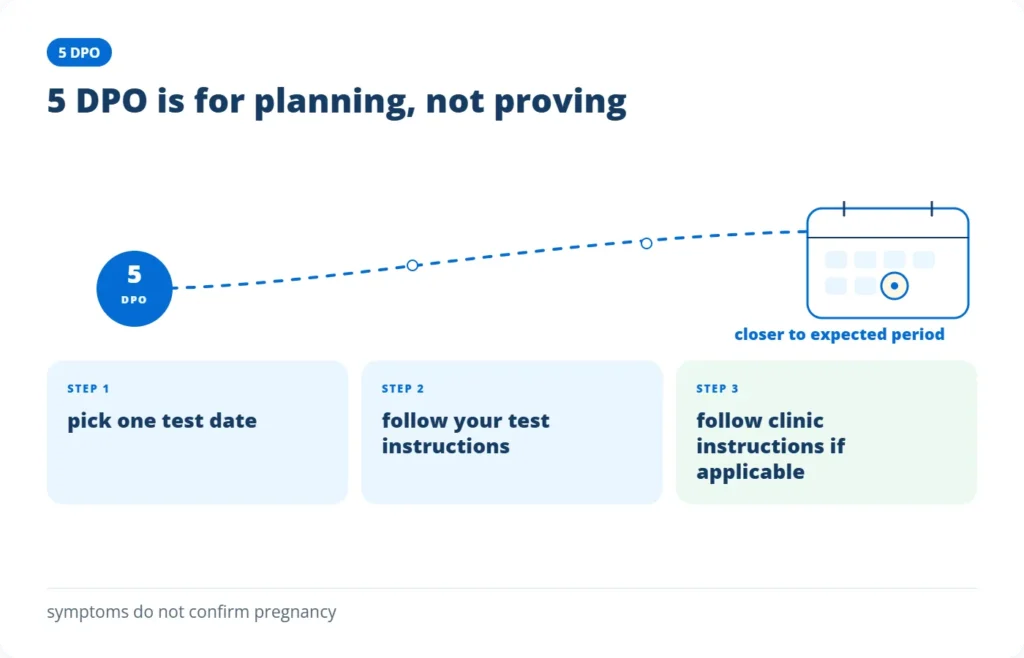
Choose one later test date from your expected period, the instructions for your exact test or your fertility clinic’s plan. If pain or bleeding concerns you, use the medical-care guidance below rather than waiting for another home test.
What does 5 DPO mean?
DPO means days past ovulation. Ovulation day is usually counted as 0 DPO, so 5 DPO describes the fifth calendar day after the day you think ovulation occurred. It is a trying-to-conceive timing label, not a direct observation of an embryo, implantation or hormone production.
If several dates are competing in your notes, the DPO calculator can place an ovulation estimate and expected period on one timeline. Its answer is still only as accurate as the date entered.
What may be happening at 5 DPO if fertilisation occurred?
If fertilisation occurred, the fertilised egg continues dividing while moving towards the uterus. Australian consumer guidance describes this journey as taking about 4 to 5 days before implantation can begin. This is a simplified sequence, not a way to locate an individual embryo from a calendar label.
An estimated 5 DPO therefore sits near the transition towards the earliest plausible implantation timing. It does not establish that implantation has started. The 6 DPO evidence decoder explains how the next day changes the timing question while keeping symptoms in perspective.
After implantation, developing placental tissue starts producing human chorionic gonadotrophin, usually shortened to hCG. The hormone then needs to reach the detection level of the blood or urine test being used. This sequence explains why a urine test is generally too early at an estimated 5 DPO without creating one universal day when every pregnancy must test positive.

Why can a 5 DPO date be uncertain?
An app predicts from previous cycle dates. A urine ovulation test detects an LH rise before ovulation. A sustained basal body temperature rise can retrospectively support that ovulation has already occurred. Clinic monitoring can support the estimate more closely, but it still does not make symptoms diagnostic or turn the DPO count into a direct biological observation.
Research using cervical mucus and basal temperature to estimate ovulation supports keeping a DPO label provisional. It does not directly observe ovulation or provide an Australian prevalence estimate or an exact timestamp for your cycle.
The 4 DPO usual-versus-new comparison explains the cycle-variation evidence in more detail. Use the page that matches your best-supported estimate rather than forcing certainty from one app date.
What can 5 DPO symptoms actually tell you?
At 5 DPO, a symptom tells you what you are feeling, not why it happened. Common luteal-phase and premenstrual experiences can overlap with sensations later remembered in a pregnancy cycle. The practical question is whether a symptom is mild and passing, or persistent, worsening or severe.
What can cramping or twinges at 5 DPO mean?
Mild cramps, pulling feelings or pelvic twinges are non-specific. At an estimated 5 DPO, they cannot confirm implantation, show where an embryo is or predict a later pregnancy-test result.
If cramps are followed by a positive test days later, the later result shows that hCG was detected later. It does not prove what caused the earlier cramp. This is the useful way to read 5 DPO symptoms ending in a BFP: the story records what someone noticed, but it does not turn the earlier sensation into a predictor for another cycle.
Can discharge, nausea, fatigue or other symptoms identify pregnancy at 5 DPO?
Discharge often becomes thicker after ovulation, but there is no validated 5 DPO discharge pattern that confirms pregnancy. Discharge with an unusual smell, irritation, bleeding or lower abdominal pain should be assessed by a doctor rather than interpreted as a pregnancy sign.
Fatigue, bloating, headache and breast tenderness can overlap with premenstrual symptoms. Nausea is also non-specific and cannot establish pregnancy. Spotting cannot be labelled implantation from timing, colour or amount alone. The guide to spotting and possible implantation explains why bleeding needs a wider context.
What does having no symptoms at 5 DPO mean?
Feeling completely normal does not show that conception failed. Early symptoms vary widely, and some people notice few or no changes before pregnancy is confirmed. Having no symptoms should not move your planned test date, just as a longer symptom list should not move it earlier.

How can you make a practical testing plan at 5 DPO?
What should you record about your estimated ovulation date?
Record whether the estimate came from an app, an LH result, a temperature shift or clinic monitoring, and keep any uncertainty with the date.
How should you choose a later pregnancy-test date at 5 DPO?
Suppose today is estimated 5 DPO and your period is expected in about nine days. A negative today could not rule pregnancy out. Check the instructions for the test you intend to use and choose one date closer to the expected period. A fertility clinic’s nominated date takes priority. The pregnancy-test timing calculator can help organise that plan.
How should you respond to symptoms at 5 DPO?
Mild symptoms can be observed without assigning them an implantation meaning. If symptoms persist, worsen or become severe, use the medical-care guidance below.
Which dates and instructions should guide your 5 DPO testing plan?
If the urge to test keeps returning, choosing one later test date can make today feel more manageable without promising what the result will be.
Use your estimated ovulation range, expected period, exact test instructions and any clinic date to choose one later test date.
This interactive guide keeps answers in the browser and does not diagnose pregnancy or replace medical care.
Most testing advice gives one vague instruction. This gives two dated points from your own cycle: the first date a positive becomes plausible, and the later date at which a negative starts to carry weight. They are different dates and they answer different questions.
Your two test dates, and what each settles
Read the guide
Your two test dates, and what each one settles
Your waiting and testing guide
Days past ovulation (DPO) is an estimate when the ovulation date is uncertain. Symptoms alone cannot tell you whether implantation or pregnancy has happened.
- Choose a useful test day. An early negative can be too soon to answer your question. Follow your exact test's instructions, or the test date your fertility clinic gave you.
- Make the result usable. Check the expiry date, required control indicator and instructions for collecting the sample. Read the result after the required wait and before the final cutoff. A later change does not replace the result read on time.
- Keep a short record. Note the test date, brand and result. Line darkness cannot tell you whether a pregnancy is progressing normally.
- Decide what happens next. If your period stays absent or results remain unclear, ask your GP or clinic about follow-up. A previous valid positive followed by a negative or unclear result needs prompt advice. Keep your clinic's medicine and follow-up plan.
Your personal next step is shown in your result. New or worsening symptoms can change what help you need; use the tool's Get advice option rather than waiting for another test.
Every outcome this tool can reach
All 6 outcomes are shown in full below. Each one names the answer that leads to it, so you can read the whole decision path without working through the questions.
Your earliest possible date
You see this when you answer “The earliest date a test could work” to “Which date do you actually need”.
Implantation occurs 6 to 12 days after ovulation and detection lags it by three to four days. The earliest end of that chain is the first date a positive is physically possible for you. It is a floor, not a forecast, and a negative on it carries no information.
The date a negative starts to count
You see this when you answer “The date a negative would mean something” to “Which date do you actually need”.
By the first day of the expected period about 90 per cent of pregnancies have implanted, and by seven days later 97 per cent. That is when a negative begins to exclude something. Roughly one in four pregnancies still test negative on that first day with a real kit, so one repeat 48 hours later completes the answer.
The whole testing window
You see this when you answer “Both, so I can plan the whole window” to “Which date do you actually need”.
Between the two dates below, testing is optional and a negative gets steadily more meaningful. Testing daily across that stretch is not useful: hCG does not change fast enough for a repeat within 48 hours to alter the answer.
- Test once on the first date only if an early positive matters to you
- Test on the second date if you want a negative to settle something
- Leave at least 48 hours between any two tests
- First morning urine on both
Without a reliable ovulation date there is no plan
You see this when you answer “I am not confident about my ovulation date” to “Which date do you actually need”.
Every date in this window is counted from ovulation. Counting from the first day of your last period and assuming day 14 is the most common source of error, because ovulation day moves with cycle length.
The highest-value action now is not a pregnancy test. It is establishing when you ovulated, or accepting that the answer will come from a period arriving or not arriving.
- A positive LH test places ovulation within a day or two
- A sustained temperature rise confirms it afterwards
- Without either, wait for the expected period rather than testing repeatedly
- A GP-arranged blood test does not depend on your cycle dates
Get the care you need
You see this when you answer “I have symptoms that worry me” to “Which date do you actually need”.
Severe abdominal or pelvic pain, heavy bleeding, shoulder-tip pain, marked dizziness, faintness or feeling very unwell need urgent medical assessment. Go to an emergency department. Call 000 for an emergency.
Worsening pain or pain lasting several hours needs urgent assessment. Abdominal pain with fever or persistent vomiting also needs urgent assessment. Get help immediately if vomiting means you cannot keep water down.
A sudden severe headache, or headache with vomiting, confusion, neck stiffness or vision changes, needs an emergency department or 000.
Do not wait for a pregnancy test. Healthdirect can help you choose care if you are unsure.
Use the clinic's test date, not a DPO plan
You see this when you answer “A fertility clinic is directing this cycle” to “Which date do you actually need”.
A clinic-directed cycle sets its own test day, chosen for the treatment you had, and an hCG trigger can produce a positive home test that reflects the medicine rather than a pregnancy for around ten to fourteen days.
A two-date plan built from a DPO count does not apply here. Testing early in a treated cycle commonly returns a result that cannot be interpreted without the clinic's context.
- Use the clinic's nominated date and method
- Tell the clinic if you have already tested and what it showed
- Do not change any prescribed medicine on the strength of a home test
- Contact the clinic if a result is unexpected in either direction
How do you know your ovulation date
This applies to Your earliest possible date; The date a negative starts to count; The whole testing window; Without a reliable ovulation date there is no plan.
- If you answered "An app or calendar prediction" to "How do you know your ovulation date": Your ovulation date came from a prediction, not an observation. App predictions commonly differ from actual ovulation by several days, so your true DPO may be lower than you think. Treat every date here as the centre of a range, not a fixed day.
- If you answered "A positive ovulation (LH) test" to "How do you know your ovulation date": A positive LH test places the surge within a day or two, and ovulation usually follows it. It narrows the estimate considerably but does not confirm an egg was released.
- If you answered "A sustained temperature rise confirmed it afterwards" to "How do you know your ovulation date": A sustained temperature rise is retrospective confirmation, the firmest anchor available at home. The dates here carry less uncertainty than any prediction.
- If you answered "I am not certain" to "How do you know your ovulation date": Without a reliable ovulation marker these dates are indicative only. If a negative result would change what you do next, a GP-arranged blood test answers independently of your cycle dates.
Worked examples
Each card shows the answers that lead to one outcome, and links to the full wording. There are 6, one for every outcome. They describe the tool, not real people, and are not medical advice.
Your earliest possible date
This answer leads here:
| Question | Answer given |
|---|---|
| Which date do you actually need? | The earliest date a test could work |
The date a negative starts to count
This answer leads here:
| Question | Answer given |
|---|---|
| Which date do you actually need? | The date a negative would mean something |
The whole testing window
This answer leads here:
| Question | Answer given |
|---|---|
| Which date do you actually need? | Both, so I can plan the whole window |
Test once on the first date only if an early positive matters to you
Without a reliable ovulation date there is no plan
This answer leads here:
| Question | Answer given |
|---|---|
| Which date do you actually need? | I am not confident about my ovulation date |
A positive LH test places ovulation within a day or two
Get the care you need
This answer leads here:
| Question | Answer given |
|---|---|
| Which date do you actually need? | I have symptoms that worry me |
Call 000 for an emergency
Use the clinic's test date, not a DPO plan
This answer leads here:
| Question | Answer given |
|---|---|
| Which date do you actually need? | A fertility clinic is directing this cycle |
Use the clinic's nominated date and method
Scroll or swipe left and right to see every example.
What this guide can tell you
These dates come from population timing applied to your ovulation estimate. They are a plan, not a prediction of the result.
Explore your next step
Choose a guide that helps with what you want to know next.
 8 DPO Symptoms and Pregnancy Tests: Test Today or Wait?Decide whether to test now or wait, and put symptoms in context.
 Faint Line on a Pregnancy Test: Is It Positive?Check the reading window and understand a faint pregnancy-test line.
 Implantation Bleeding: Colour, Flow, Timing and When to TestUnderstand what spotting can and cannot tell you.
 How Long Does Ovulation Last? Fertile Window and Best Days to ConceiveUnderstand the fertile window and the limits of timing estimates.
How should you interpret a pregnancy test at 5 DPO?
Home pregnancy tests measure hCG in urine. At an estimated 5 DPO, a negative result usually reflects the timing of the test rather than the final cycle outcome. It cannot rule pregnancy out, and repeating several tests on the same early day does not overcome the biological timing limit.
Australian home-testing guidance generally centres on the expected period because urine hCG is more likely to be detectable by then. Testing instructions still matter because devices can differ in sample method, criteria for a positive result and reading time. A clinic-directed schedule takes priority after fertility treatment.
What if the result looks positive at an estimated 5 DPO?
First, recheck the ovulation estimate and the device’s valid reading window. Ovulation may have occurred earlier than an app predicted. A mark first noticed after the valid window should not be used as a new positive result. The guide to evaporation lines and late test changes explains how to handle marks that appear after the reading window.
If the required control appeared and the correct test area meets that device’s criteria for a positive result within its valid reading window, arrange confirmation and follow-up with a GP or fertility clinic, including for a faint positive. If the required control is absent or the device reports an error, the result is invalid: use a new, unexpired device according to its instructions. The Australian guide to what to do after a positive pregnancy test explains the next care step.
Recent fertility treatment can change interpretation. Follow your clinic’s testing and medicine plan, contact the clinic about an unexpected result and do not stop prescribed medicines without advice. The Ovidrel and trigger shot guide explains why an hCG-containing trigger can affect an early result.
When should you seek medical care in Australia?
See a doctor if abdominal or pelvic pain keeps returning or is ongoing. Arrange GP assessment for bleeding between periods or after sex, even if it is light, and for unusual discharge with irritation or lower abdominal pain. The estimated DPO date should not delay assessment.
Seek urgent medical attention if pain is getting worse, has lasted for several hours, occurs with a fever of 38°C or higher, or is accompanied by persistent vomiting.
If pregnancy is possible, severe abdominal or pelvic pain, shoulder-tip pain, heavy bleeding, marked dizziness, fainting or feeling very unwell needs immediate emergency assessment. Go to the nearest hospital emergency department or call triple zero (000) for an ambulance. A positive pregnancy test is not required before using this route.
A negative home pregnancy test this early cannot identify the cause of pain or bleeding and must not be used as reassurance against urgent assessment. Symptoms should be judged on their own severity, not used to diagnose or exclude ectopic pregnancy from a DPO label.
Frequently asked questions about 5 DPO symptoms in Australia
Is 5 DPO the same as being five days pregnant?
No. DPO counts forward from an estimated ovulation day. Australian pregnancy care counts gestational age from the first day of the last menstrual period, usually about 2 weeks before conception. They are different timelines.
Does a positive ovulation test prove I am exactly 5 DPO?
No. A positive urine ovulation test detects an LH rise and usually suggests ovulation may occur within the next 24 to 36 hours. It narrows the likely window but does not identify the exact time ovulation occurred.
Can a blood hCG test confirm pregnancy at 5 DPO?
Blood hCG testing is more sensitive than urine testing, but an estimated 5 DPO may still be before placental hCG is detectable. A clinician should decide whether a blood test is useful for your circumstances.
Does first-morning urine make a 5 DPO test reliable?
No. First-morning urine is usually more concentrated and may reduce dilution-related false negatives, but it cannot make hCG detectable before enough hormone is present. A 5 DPO negative result remains too early to rule pregnancy out.
Should I change fertility medicines because of a 5 DPO test?
No. Do not stop or change prescribed fertility medicines because of an early home result. Follow your clinic’s plan. An hCG trigger such as Ovidrel can interfere with urine or blood hCG testing for up to 10 days after administration.
Can spotting at 5 DPO confirm implantation?
No. Timing, colour or amount cannot confirm that spotting came from implantation. Arrange GP assessment for bleeding between periods or after sex, even if it is light. Heavy bleeding needs immediate emergency assessment. Severe abdominal or pelvic pain, shoulder-tip pain, marked dizziness, fainting or feeling very unwell also requires an emergency department or 000.
Next Steps in Australia
If you feel well, keep the ovulation clue and the later test date you chose together. Let the next appropriately timed test answer the pregnancy question, while any symptom that needs care is assessed on its own merits.
A single plan is usually easier to follow than repeated symptom checks. You can return to it when the test date arrives or sooner if a symptom needs medical attention.
Last reviewed: 20 September 2026
Next scheduled review: September 2027
References
Fertility2Family articles are researched using Australian Government health guidance, professional clinical recommendations and peer-reviewed medical literature. The references below were used to research and medically review this article and provide additional reading for readers who want to explore the evidence in more detail.
You can read how we research, write and check our health information in our editorial and medical review policy, and see who reviews our articles and their clinical credentials.
Pregnancy, Birth and Baby Ovulation and fertility
Australian guidance on ovulation timing, urinary LH tests and basal body temperature, showing why home tracking can narrow a window without proving an exact ovulation time.
Pregnancy, Birth and Baby Conception – from fertilisation to embryo
Australian infographic text describing the fertilised egg’s four-to-five-day journey through the fallopian tube towards the uterus before implantation can begin.
Pregnancy, Birth and Baby hCG levels
Australian guidance explaining that developing placental tissue produces hCG after implantation and that urine or blood detection depends on timing, hormone concentration and the test used.
Pregnancy, Birth and Baby Pregnancy tests
Australian guidance on home pregnancy testing, expected-period timing, early false-negative results, device instructions and clinical follow-up after positive or uncertain results.
Pregnancy, Birth and Baby Anatomy of pregnancy and birth
Australian consumer guidance explaining that gestational age is counted from the first day of the last menstrual period rather than from ovulation or conception.
Healthdirect Australia Premenstrual syndrome (PMS)
Australian guidance describing fatigue, bloating, headache and breast tenderness among common premenstrual experiences, supporting caution when interpreting the same symptoms as pregnancy evidence.
Healthdirect Australia Nausea
Australian guidance explaining that nausea is non-specific and can have many causes, including illness, medicines, pain, stress, food-related factors and pregnancy.
Pregnancy, Birth and Baby Early signs of pregnancy
Australian guidance showing that early pregnancy symptoms vary widely and that some people notice few or no symptoms before pregnancy is confirmed.
Healthdirect Australia Vaginal discharge
Australian guidance on normal cycle-related discharge changes, including thicker discharge after ovulation, and changes such as unusual smell, irritation, bleeding or pain requiring assessment.
Healthdirect Australia Vaginal bleeding
Australian guidance stating that bleeding between periods or after sex should be assessed by a doctor and explaining that vaginal bleeding can have several causes.
Healthdirect Australia Abdominal pain
Australian guidance distinguishing recurrent pain from urgent attention for worsening or prolonged pain, or pain with fever or persistent vomiting, and immediate emergency care for severe pain.
Healthdirect Australia Ectopic pregnancy
Australian guidance on pain, bleeding, shoulder-tip pain, dizziness and faintness, with emergency-department or 000 access for strong symptoms or feeling unwell when pregnancy is possible.
Better Health Channel, Victorian Department of Health Pregnancy testing
Victorian public-health guidance on first-morning urine, early false negatives, blood-test sensitivity and GP confirmation of a positive home result, including a faint positive.
Therapeutic Goods Administration Meeting clinical evidence requirements for in-vitro diagnostic (IVD) medical devices
Australian regulatory guidance using pregnancy-test control lines to explain that a missing control means the test is invalid and should be repeated with a different device.
Australian Commission on Safety and Quality in Health Care Ovidrel Pen
Current Australian product information stating that, after administration, Ovidrel may interfere with serum or urine hCG testing for up to ten days and cause a false-positive result.
Human Reproduction Variations in ovulation time and menstrual cycle characteristics: analysis of a prospective long-term cohort study
A 2026 paper analysing prospective cycle records collected from 1985 to 2019, with ovulation estimated from cervical mucus and basal temperature patterns across 12 cycles.
Sources for the interactive tool
Every figure the interactive tool on this page displays is traceable to the sources below. Australian clinical review of this exact wording is pending and the tool does not replace advice from a qualified clinician.
- Time of implantation of the conceptus and loss of pregnancy, New England Journal of Medicine. N Engl J Med. 1999;340(23):1796-9. doi:10.1056/NEJM199906103402304. View source
- Natural limits of pregnancy testing in relation to the expected menstrual period, JAMA. JAMA. 2001;286(14):1759-61. doi:10.1001/jama.286.14.1759. View source
- Pregnancy tests: a review, Human Reproduction. Hum Reprod. 1992;7(5):701-10. View source
- hCG test, Healthdirect Australia. View source
- Fertility awareness and natural family planning, Healthdirect Australia. View source
- Ectopic pregnancy, Healthdirect Australia. View source
- In vitro diagnostic devices, Therapeutic Goods Administration. View source
- Pregnancy-test strip instructions (PDF), Fertility2Family product instructions. View source
- Pregnancy-test midstream instructions (PDF), Fertility2Family product instructions. View source