

At 6 DPO, cramps, nausea, fatigue, spotting or a change in discharge can feel significant, but none can tell you whether you are pregnant. It is usually too early for a useful negative result from a home pregnancy test, while an unexpectedly early positive needs its timing, control and reading window checked.
This guide separates three things that are often blurred together: what research observed, what a symptom can tell you and what a valid home test can establish.
Quick answers about 6 DPO symptoms
What can symptoms mean at 6 DPO?
Cramps, nausea, tiredness, spotting, breast changes or creamy discharge can occur at 6 DPO, but they cannot reliably distinguish a pregnant cycle from a non-pregnant cycle. Symptom severity can guide whether you need care, not whether implantation occurred.
Is 6 DPO too early for a pregnancy test?
Usually, yes. A valid negative means the test did not detect hCG in that sample; at 6 DPO, it cannot rule pregnancy out. Follow your exact device’s instructions and use your expected period or fertility-clinic plan to choose a more useful testing point.
When do pain or bleeding need urgent care?
Severe abdominal or pelvic pain, heavy bleeding, fainting, marked dizziness or feeling very unwell require emergency care. Go to your nearest emergency department or call 000 for an ambulance. Another negative test should not delay assessment.
What does 6 DPO mean, and how certain is the date?
DPO means days past ovulation. Ovulation day is counted as 0 DPO, so 6 DPO is six calendar days later. This differs from the gestational age used in Australian maternity care, which begins from the first day of the last menstrual period.
The number is only as reliable as the ovulation estimate. An app predicts from previous cycles. A positive urine LH test usually shows that ovulation may be approaching, but it does not record the exact moment the egg was released. A sustained basal body temperature rise gives retrospective support. Ultrasound or hormone monitoring in a treatment cycle supplies a different level of timing information without making an exact spontaneous-conception DPO count automatic.
The DPO calculator can place your ovulation clues on one timeline. If recalculating your ovulation estimate places you at 5 DPO rather than 6 DPO, the practical 5 DPO wait-and-test plan explains why that point remains before the earliest urinary hCG observation used here.
What did the 6 DPO implantation study actually measure?
In the foundational prospective study, researchers collected daily urine samples. Among 141 pregnancies that lasted at least six weeks after the first day of the last menstrual period, first urinary hCG appeared 6 to 12 days after ovulation. Day 6 was the earliest observation of first urinary hCG in that group.
That result supports an early research boundary, not directly observed embryo attachment. The study defined implantation timing through the first appearance of urinary hCG, so it cannot show that implantation occurred on day 6 in a particular person. It also cannot promise that a retail home test will detect pregnancy on the same day as the research assay.
The study is older and was conducted outside Australia. Its biological timing observation can still inform this question, while current Australian guidance, the instructions for the exact home test and any fertility-clinic protocol control the practical next step.
How do research findings, symptoms and home tests differ at 6 DPO?
| Observation or measurement | What it supports | What it cannot establish |
|---|---|---|
| First urinary hCG in daily research samples | An early timing boundary in that study group. | Direct embryo attachment timing or a retail-test result. |
| A personal symptom | What you are experiencing and whether severity changes the care needed. | Pregnancy or implantation. |
| A home urine test with a valid control, used and read as directed | Whether that device detected hCG in that sample and reading window. | Implantation timing, pregnancy location or viability. |

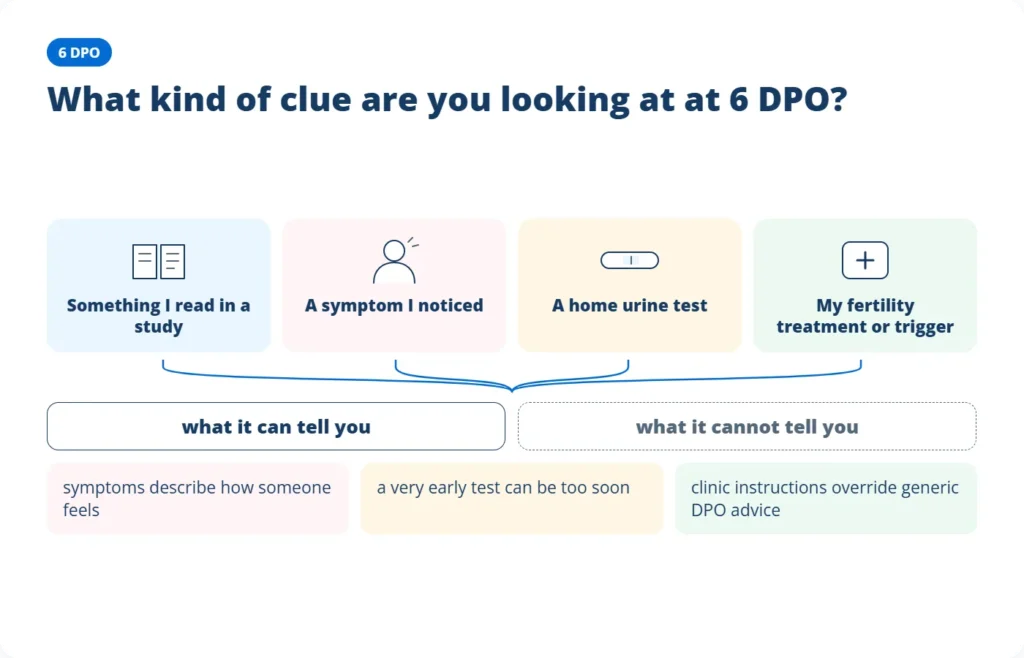
What kind of evidence are you interpreting at 6 DPO?
Early-pregnancy research can sound personal when you are waiting for your own answer. This decoder separates a study finding, a body sensation, a home test and a clinic instruction.
Check what a research finding, symptom, home test or treatment instruction can and cannot tell you.
This interactive guide keeps answers in the browser and does not diagnose pregnancy or replace medical care.
The article already explains what the implantation research observed. What it cannot do is place your specific dates inside that distribution. This converts the published day-by-day figures into dated positions for your cycle, and states plainly how much confidence each one deserves.
Place your dates in the research distribution
Read the guide
Where your cycle sits in the research distribution
Your waiting and testing guide
Days past ovulation (DPO) is an estimate when the ovulation date is uncertain. Symptoms alone cannot tell you whether implantation or pregnancy has happened.
- Choose a useful test day. An early negative can be too soon to answer your question. Follow your exact test's instructions, or the test date your fertility clinic gave you.
- Make the result usable. Check the expiry date, required control indicator and instructions for collecting the sample. Read the result after the required wait and before the final cutoff. A later change does not replace the result read on time.
- Keep a short record. Note the test date, brand and result. Line darkness cannot tell you whether a pregnancy is progressing normally.
- Decide what happens next. If your period stays absent or results remain unclear, ask your GP or clinic about follow-up. A previous valid positive followed by a negative or unclear result needs prompt advice. Keep your clinic's medicine and follow-up plan.
Your personal next step is shown in your result. New or worsening symptoms can change what help you need; use the tool's Get advice option rather than waiting for another test.
Every outcome this tool can reach
All 4 outcomes are shown in full below. Each one names the answer that leads to it, so you can read the whole decision path without working through the questions.
Your dates against the distribution
You see this when you answer “Put my dates against the distribution” to “What do you want to do with the research figures”.
The dates below convert the published distribution into your calendar. Day 8, 9 and 10 after ovulation account for 84 per cent of implantations in ongoing pregnancies, with a mean of 9.1 days, and detection lags that by about three to four days.
This places your cycle against the distribution. It does not locate you within it, and no home measurement can.
- If you answered "App or calendar only" to "How firm is your ovulation date": Every date below inherits the error in an app prediction. If your true ovulation was two days later, the whole distribution shifts two days with it and an early negative means even less.
- If you answered "A positive LH test" to "How firm is your ovulation date": An LH surge places ovulation within a day or two, so the mapping holds reasonably well. The surge still does not confirm release.
- If you answered "Confirmed by a temperature rise" to "How firm is your ovulation date": A confirmed temperature rise is the firmest anchor available at home, so the mapping below is as accurate as this method allows.
- If you answered "Not certain" to "How firm is your ovulation date": Without an ovulation anchor the distribution cannot be mapped to a calendar at all. Treat the dates as illustrative only.
What the day 6 figure actually is
You see this when you answer “Understand what the day 6 boundary really means” to “What do you want to do with the research figures”.
Day 6 is the earliest day on which first urinary hCG was observed in the study cohort, not a day on which implantation is common. It marks the edge of what was measured, which is a very different claim from a day worth testing on.
Quoting day 6 as an implantation day, rather than as the earliest observation in a distribution, is the most common misreading of this research.
- The measurement was first urinary hCG, not directly observed attachment
- Day 6 was the boundary of observation, not a typical day
- Detection still lags first hCG production
- An early boundary is not a testing recommendation
What later implantation changes
You see this when you answer “What later implantation means” to “What do you want to do with the research figures”.
Implantation after day 10 was associated with a higher rate of early loss in the same cohort. That is a population association, not a prediction about an individual cycle, and it cannot be acted on at home.
The practical consequence is narrower: later implantation pushes your detection date later, so a negative that looks late may simply be early for your cycle.
- If you answered "App or calendar only" to "How firm is your ovulation date": If your ovulation date is a prediction, a detection date that looks late may only be late for the date you assumed. Recount from the strongest evidence you have before drawing any conclusion.
- If you answered "Not certain" to "How firm is your ovulation date": Without an ovulation anchor there is no way to tell late implantation from a wrong DPO count. A blood test through your GP answers independently of your dates.
Get the care you need
You see this when you answer “I have symptoms that worry me” to “What do you want to do with the research figures”.
Severe abdominal or pelvic pain, heavy bleeding, shoulder-tip pain, marked dizziness, faintness or feeling very unwell need urgent medical assessment. Go to an emergency department. Call 000 for an emergency.
Worsening pain or pain lasting several hours needs urgent assessment. Abdominal pain with fever or persistent vomiting also needs urgent assessment. Get help immediately if vomiting means you cannot keep water down.
A sudden severe headache, or headache with vomiting, confusion, neck stiffness or vision changes, needs an emergency department or 000.
Do not wait for a pregnancy test. Healthdirect can help you choose care if you are unsure.
Worked examples
Each card shows the answers that lead to one outcome, and links to the full wording. There are 4, one for every outcome. They describe the tool, not real people, and are not medical advice.
Your dates against the distribution
This answer leads here:
| Question | Answer given |
|---|---|
| What do you want to do with the research figures? | Put my dates against the distribution |
What the day 6 figure actually is
This answer leads here:
| Question | Answer given |
|---|---|
| What do you want to do with the research figures? | Understand what the day 6 boundary really means |
The measurement was first urinary hCG, not directly observed attachment
What later implantation changes
This answer leads here:
| Question | Answer given |
|---|---|
| What do you want to do with the research figures? | What later implantation means |
Get the care you need
This answer leads here:
| Question | Answer given |
|---|---|
| What do you want to do with the research figures? | I have symptoms that worry me |
Call 000 for an emergency
Scroll or swipe left and right to see every example.
What this guide can tell you
This maps population figures onto your dates. It cannot tell you where in the distribution your cycle actually sits, and it produces no probability.
Explore your next step
Choose a guide that helps with what you want to know next.
 8 DPO Symptoms and Pregnancy Tests: Test Today or Wait?Decide whether to test now or wait, and put symptoms in context.
 Faint Line on a Pregnancy Test: Is It Positive?Check the reading window and understand a faint pregnancy-test line.
 Implantation Bleeding: Colour, Flow, Timing and When to TestUnderstand what spotting can and cannot tell you.
 How Long Does Ovulation Last? Fertile Window and Best Days to ConceiveUnderstand the fertile window and the limits of timing estimates.
Why do symptoms overlap at 6 DPO?
Post-ovulation hormone changes occur whether or not the cycle later results in pregnancy, which helps explain the symptom overlap. The fertility hormone guide explains progesterone’s role and how hormone tests are interpreted.
Mild cramps, fatigue, breast tenderness or bloating can therefore be genuine without identifying their cause. A cramp cannot show where an embryo is. Spotting should not be labelled implantation bleeding from timing or colour alone; the implantation bleeding guide explains why appearance cannot establish the source.
Discharge can also change after ovulation, but no appearance at 6 DPO can confirm pregnancy. Use it as cycle context rather than a pregnancy test.
BFP is shorthand for a positive pregnancy test. A later positive shows that hCG eventually became detectable. It does not prove that a cramp, wave of nausea or discharge change at 6 DPO predicted the result.
What can a 6 DPO pregnancy test tell you?
A home pregnancy test checks urine for hCG. At a true 6 DPO, implantation may not have occurred, or hCG may be below the device’s detection threshold. If the control indicator appears and the test was used and read as directed, a negative result means that the device did not detect hCG in that sample at that time. It cannot rule out a pregnancy that may become detectable later. A result without a valid control is invalid and cannot be interpreted as negative. Use a fresh, unexpired device according to its instructions when you next test.
Use the expected-period timing and repeat-testing directions supplied with your exact device rather than applying one universal interval. The timing calculator for a more informative test date can help you choose a testing point from your ovulation clue or expected period without turning 6 DPO into a promise of early detection.
If a test is positive this early, confirm that the control indicator is present and that the result appeared within the manufacturer’s stated reading window. A correctly used, valid in-window positive supports that hCG was detected. It cannot show when implantation occurred, where a pregnancy is located or whether it is developing normally.
An unexpectedly early positive can mean that ovulation occurred earlier than estimated or that an hCG-containing fertility medicine is affecting the result. A mark first noticed after the reading window should not be treated as a fresh positive; the evaporation-line guide explains why line timing matters. After a valid positive, contact your GP or fertility clinic for confirmation and the next care step. Tell them about any hCG trigger or recent pregnancy, including a recent birth or pregnancy loss. The Australian positive-pregnancy-test pathway explains what to expect. Do not use line darkness as a health check.

What changes if you used an hCG trigger or had an embryo transfer?
Treatment-cycle results need the fertility clinic’s timeline. Ovidrel contains choriogonadotropin alfa, and current Australian medicine information states that it may interfere with serum or urine hCG testing for up to ten days after administration and lead to a false-positive pregnancy test. The Ovidrel and trigger-shot guide explains the testing issue, but the clinic’s nominated test date takes priority.
Do not stop or change prescribed medicine because of a home result. Embryo-transfer dates also describe a different developmental timeline from spontaneous-conception DPO, so use the test date and medicine instructions supplied by the treating clinic rather than converting the transfer into an ordinary 6 DPO count.
When should 6 DPO symptoms be assessed in Australia?
Mild, brief symptoms can usually be observed without interpreting them as evidence of pregnancy. Seek urgent medical attention if abdominal or pelvic pain is worsening, lasts several hours, or occurs with fever or persistent vomiting. Arrange GP advice for recurring symptoms, unusual discharge, urinary symptoms, or other changes that concern you. Bleeding between periods or after sex should also be assessed by a GP, even when it is light. Contact your fertility clinic about symptoms or unexpected results during a monitored cycle.
If you have severe abdominal or pelvic pain, heavy bleeding, shoulder-tip pain, fainting, marked dizziness or feel very unwell, go to your nearest emergency department or call 000 for an ambulance. These symptoms need assessment on their own merits. A DPO label does not diagnose an ectopic pregnancy, and a negative home test must not delay urgent care.

Frequently asked questions about 6 DPO symptoms in Australia
Are cramps at 6 DPO a good sign or a bad sign?
Cramps alone are neither a good nor bad sign, and at 6 DPO they cannot predict a later result. The care section above explains when the pattern or severity needs assessment.
When does discharge at 6 DPO need medical advice?
Clear, white or creamy discharge without a strong smell can occur as part of normal cycle variation. See a GP if it looks or smells different from what is usual for you, or comes with itching, pain, bleeding, lower abdominal pain or fever. The milky white discharge guide explains these care cues in more detail.
Why can nausea happen at 6 DPO?
Nausea has many possible causes, including illness, medicines and food-related causes. At 6 DPO it cannot identify pregnancy. Seek immediate medical attention from a doctor or emergency department if you cannot keep water down, can manage only a few sips, or have signs of dehydration. Seek medical advice for ongoing vomiting.
Can a positive pregnancy test at 6 DPO tell me if it is twins?
The test cannot tell you. Home tests detect whether hCG is present above the device threshold; they do not show whether a pregnancy is singleton or multiple. Even a measured high hCG level has more than one possible explanation. Multiple pregnancy is confirmed by ultrasound, not by an early home-test line.
Does having no symptoms at 6 DPO mean anything?
It does not provide a pregnancy answer. Some cycles that later produce a positive test are symptom-free at 6 DPO, while symptoms can occur in cycles that do not. There is no useful 6 DPO symptom score.
What should I record before asking about an unexpected 6 DPO result?
If you are contacting a GP or fertility clinic about symptoms or an unexpected result, note the test date and time, the device and reading window, how ovulation was estimated, and any hCG trigger or embryo-transfer dates.
Next Steps in Australia
If you are 6 DPO today, the 7 DPO uncertainty plan continues the day-by-day timeline and explains what changes on the next day of the wait. If day-by-day checking makes the wait harder, use the two-week-wait stage navigator instead.
Research can describe groups, but it cannot settle one person’s result today. Keep the evidence categories separate and let the correctly timed test or clinical plan answer the next question.
Last reviewed: 20 September 2026
Next scheduled review: September 2027
References
Fertility2Family articles are researched using Australian Government health guidance, professional clinical recommendations and peer-reviewed medical literature. The references below were used to research and medically review this article and provide additional reading for readers who want to explore the evidence in more detail.
You can read how we research, write and check our health information in our editorial and medical review policy, and see who reviews our articles and their clinical credentials.
Pregnancy, Birth and Baby
Ovulation and fertility
Australian guidance on ovulation, cycle variation, cervical mucus, basal body temperature and urinary LH testing, including the limits of using home signs to estimate exact timing.
Pregnancy, Birth and Baby
Conception and fetal development
Australian guidance on fertilisation, early embryo development, implantation and pregnancy dating from the first day of the last menstrual period used in maternity care.
Healthdirect Australia
Fertility awareness (natural family planning)
Australian guidance on calendar, mucus and temperature tracking, including circumstances that make home estimates less reliable and why no single method provides an exact ovulation timestamp.
New England Journal of Medicine
Time of implantation of the conceptus and loss of pregnancy
Prospective daily urine-hCG research reporting first urinary hCG 6 to 12 days after ovulation among 141 pregnancies lasting at least six weeks after the first day of the last menstrual period.
Queensland Health
Periods
Queensland Health explanation of the luteal phase, corpus luteum and progesterone production after ovulation, supporting the shared post-ovulation biology behind overlapping cycle symptoms.
Healthdirect Australia
Premenstrual syndrome (PMS)
Australian guidance describing second-half cycle symptoms such as bloating, breast tenderness, headache and fatigue, supporting why post-ovulation symptoms are not specific to pregnancy.
Pregnancy, Birth and Baby
Early signs of pregnancy
Australian consumer guidance on variable early pregnancy symptoms, including nausea, tiredness and breast changes, while noting that some people notice few or no early symptoms.
Healthdirect Australia
Human chorionic gonadotropin (hCG) test – pregnancy
Australian guidance on qualitative urine and quantitative blood hCG testing, following device instructions, early false negatives and medical checking when a home result seems incorrect.
Healthdirect Australia
hCG levels
Australian guidance on home-test timing, early false negatives, wide hCG variation and why an early hCG result alone cannot identify a multiple pregnancy.
Better Health Channel
Pregnancy testing
Victorian Government guidance on test instructions, positive-result confirmation, repeat urine or blood testing, and how recent birth, pregnancy loss or fertility medicines can affect interpretation.
Healthdirect Australia
Vaginal discharge
Australian guidance on normal cycle-related discharge and the changes in smell, colour, texture or associated pain, itching, bleeding and fever that warrant medical advice.
Healthdirect Australia
Nausea
Australian guidance describing varied causes of nausea, including infection, medicines and food-related causes, plus when persistent nausea or severe associated symptoms need assessment.
Healthdirect Australia
Vomiting – treatments, self-care and causes
Australian guidance requiring immediate medical attention when vomiting prevents retaining water or more than a few sips, causes dehydration or occurs with fever, and advising review for ongoing vomiting.
Healthdirect Australia
Abdominal pain – causes, self-care and treatments
Australian guidance distinguishing routine review from urgent assessment for worsening or prolonged pain and immediate emergency-department or ambulance care for severe abdominal pain.
Healthdirect Australia
Ectopic pregnancy
Australian guidance on bleeding, abdominal or shoulder-tip pain, dizziness and faintness, including emergency-department or ambulance access for concerning symptoms during pregnancy.
Australian Commission on Safety and Quality in Health Care
Ovidrel Pen
Current Australian medicine information stating that Ovidrel may interfere with serum or urine hCG testing for up to ten days after administration and lead to a false-positive pregnancy test.
South Eastern Sydney Local Health District, Royal Hospital for Women
In Vitro Fertilisation (IVF) – Embryo Transfer
A NSW hospital protocol showing that embryo-transfer timing, pregnancy testing and luteal-support decisions are managed through the treating clinical team rather than spontaneous-conception DPO charts.
Healthdirect Australia Bleeding between periods
Australian guidance advising GP assessment for bleeding between periods or after sex, including light spotting, with emergency care for heavy bleeding or faintness.
Therapeutic Goods Administration Meeting clinical evidence requirements for in-vitro diagnostic (IVD) medical devices
Australian device guidance explaining that a missing required pregnancy-test control makes the result invalid and requires retesting with another device.
Sources for the interactive tool
Every figure the interactive tool on this page displays is traceable to the sources below. Australian clinical review of this exact wording is pending and the tool does not replace advice from a qualified clinician.
- Time of implantation of the conceptus and loss of pregnancy, New England Journal of Medicine. N Engl J Med. 1999;340(23):1796-9. doi:10.1056/NEJM199906103402304. View source
- Natural limits of pregnancy testing in relation to the expected menstrual period, JAMA. JAMA. 2001;286(14):1759-61. doi:10.1001/jama.286.14.1759. View source
- Pregnancy tests: a review, Human Reproduction. Hum Reprod. 1992;7(5):701-10. View source
- hCG test, Healthdirect Australia. View source
- Fertility awareness and natural family planning, Healthdirect Australia. View source
- Ectopic pregnancy, Healthdirect Australia. View source
- In vitro diagnostic devices, Therapeutic Goods Administration. View source
- Pregnancy-test strip instructions (PDF), Fertility2Family product instructions. View source
- Pregnancy-test midstream instructions (PDF), Fertility2Family product instructions. View source